The daily positivity rate is the percentage of positive COVID-19 test results for each 24 hour period. The rate adjusts for the number of tests which varies from day to day.
The daily positivity rate is a useful metric, but an imperfect one. As I’ve said in previous posts, we need a proper epidemiologic study of COVID-19.
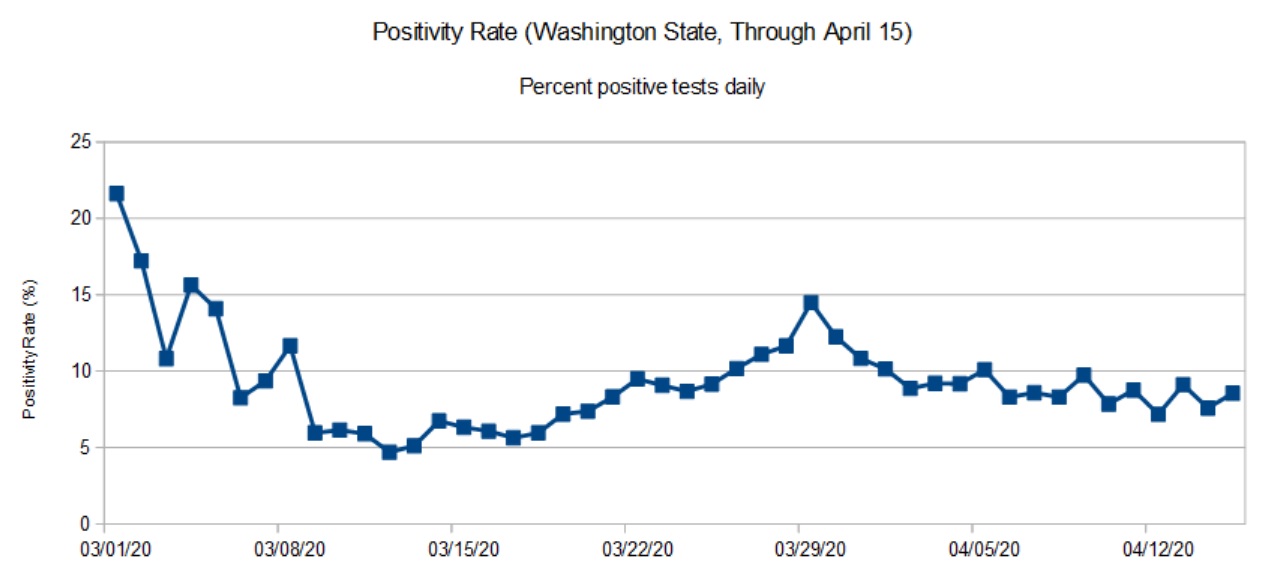
The first graph (below) is the daily positivity rate for Washington State though April 15. Why April 15 and not today, 24 April 2020? The Department of Health does not guarantee complete data for the most recent days. The data through April 15 is (nearly) complete although a few test results still trickle in.
Washington State daily positivity rate (April 15, 2020)
As noted in the graph posted last week, the state is past the peak and is in a slow decline. The peak occurred in late March. The daily positivity rate has declined to where it was in mid-March.
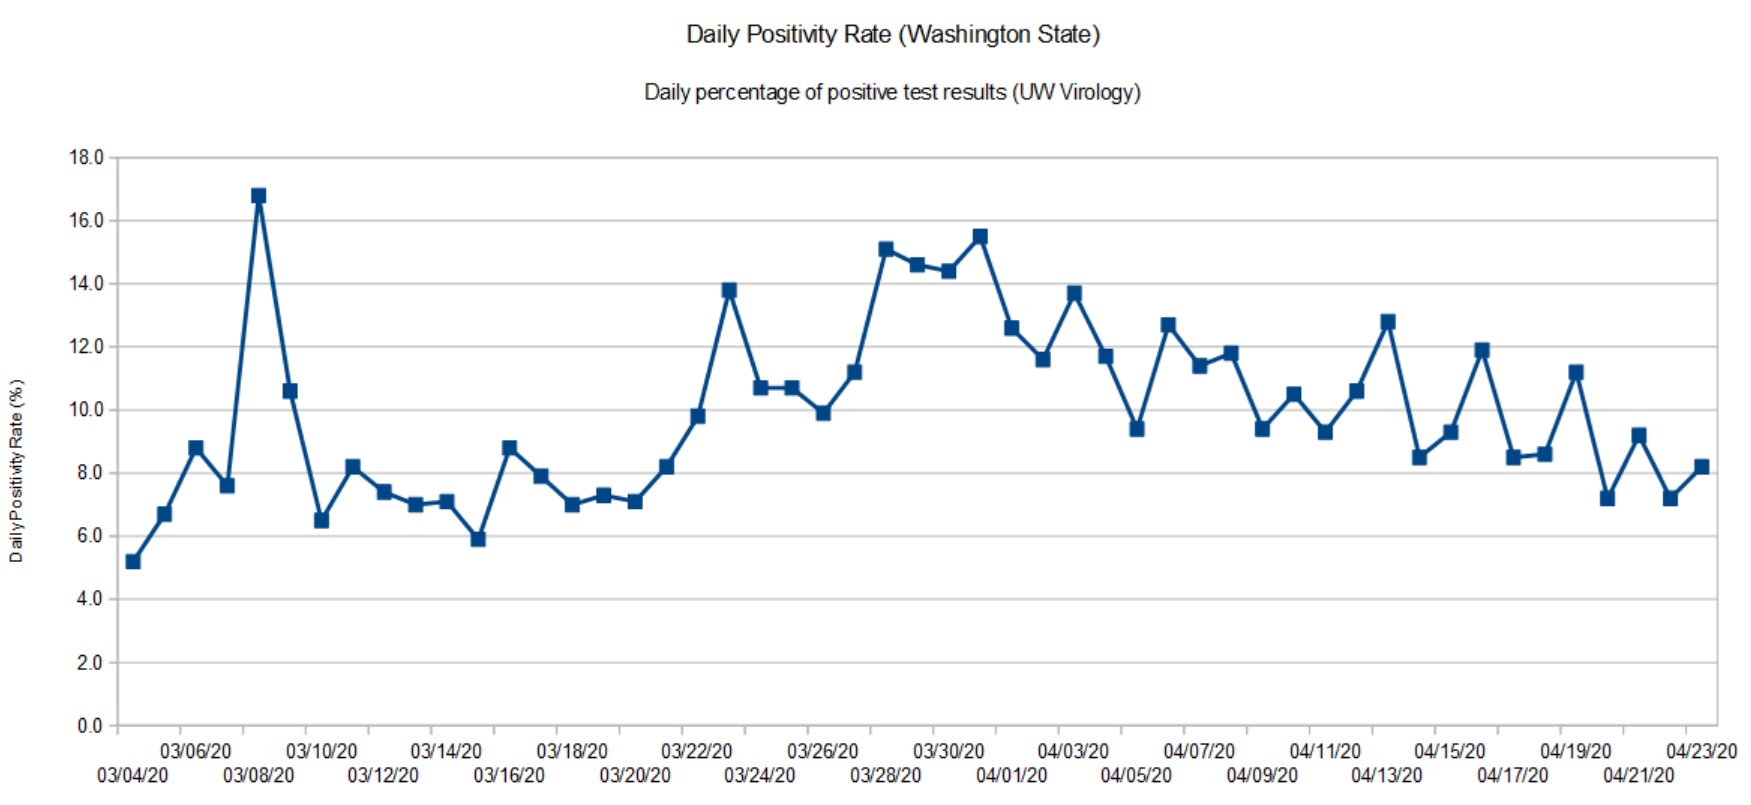
For comparison, here is the data from the UW Virology Lab. UW performs testing for and county and state health authorities. [Click images to enlarge.]
University of Washington positivity rate (April 23, 2020)
The shape of the graph is consistent with the overall state data. The Virology Lab data is up-to-date since they just report daily results for the lab itself (samples in, results out).
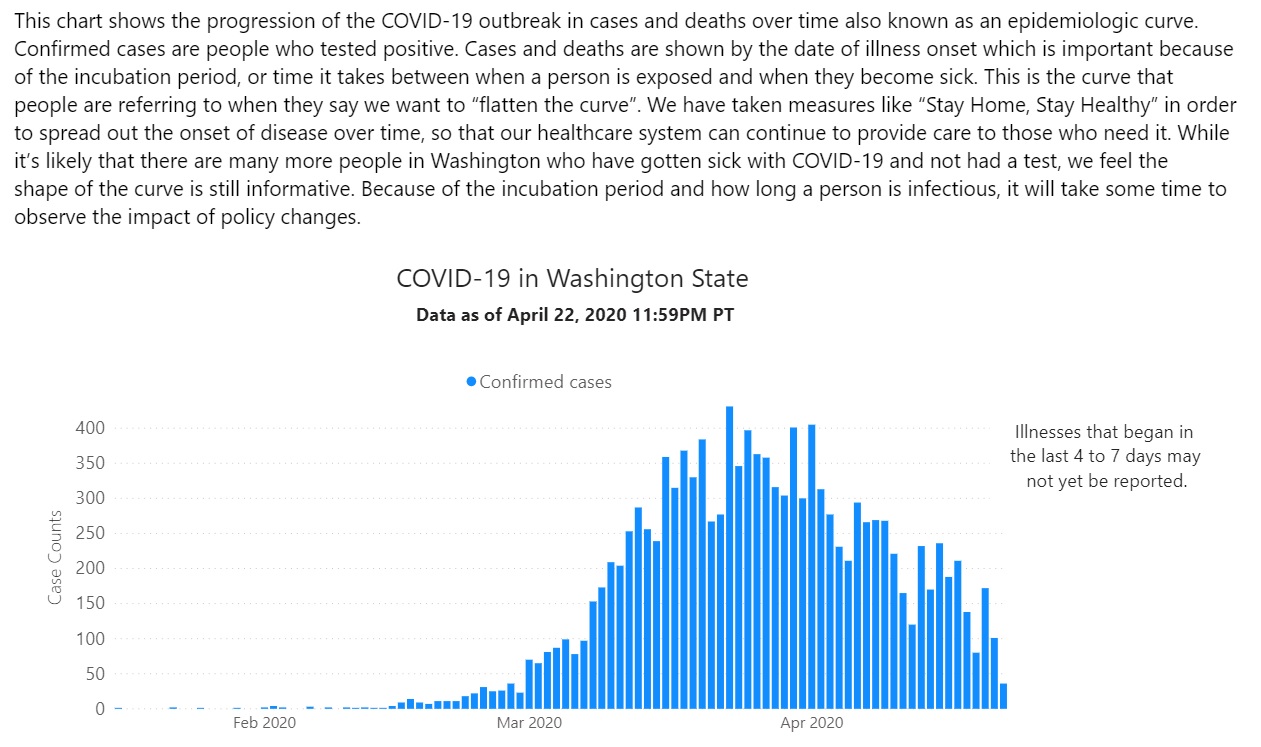
The Washington State epidemiologic curve (below) is informative, too. Known cases are tallied by the date of illness onset.
Washington State epidemiologic curve (April 22, 2020)
The epidemiologic curve shows a steady decline due to community mitigation, also known as “social distancing.” This is good news.
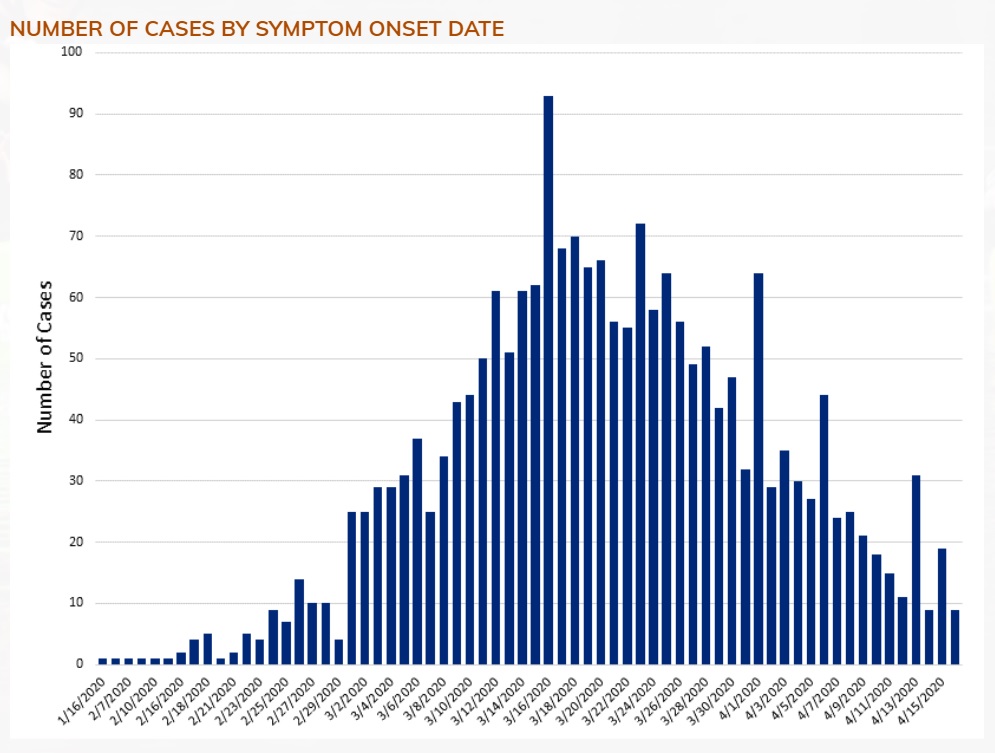
To complete the picture, here is the epidemiologic curve for Snohomish County, where I live.
Snohomish Country epidemiologic curve (April 15,2020)
Snohomish County shows a similar decline in new confirmed cases. Again, this is good news.
The big question for Governor Inslee and other decision makers is “How low is enough?” The answer to this question determines when social distancing can be relaxed. Currently, social distancing is expected to be in place until May 4th at the earliest. Hopefully, Washington will beef up contact tracing and isolation over the next two weeks. Then, it’s whack-a-mole.
Stay distant and stay healthy. Science works — P.J. Drongowski
My weekly chart showing the positivity rate for Washington State is a tad late. The Washington Department of Health (DOH) has been busy fixing and upgrading its web site. The new site is a quite an improvement with informative charts, graphs and tables.
Looking at their data, I can appreciate the depth of their collection and reporting problems. Their old database was a “peacetime” tool, collecting positive results from a few of Washington’s many counties. In the fight against COVID-19, all counties are reporting at once and epidemiologists and decision makers want and need additional data about the number of tests, sex, age, etc. Of course, doing all of this work in the middle of a crisis must raise the IT stress level!
The state DOH site now reports detailed testing information in the form of a bar chart. The bar chart shows the number of positive and negative tests each day based on specimen date. This is a meaningful time base as it allows a snapshot of the positivity rate on a given day. It’s much harder to organize test data in this way than just lumping test results willy-nilly as they come in. (See “stress level” above.)
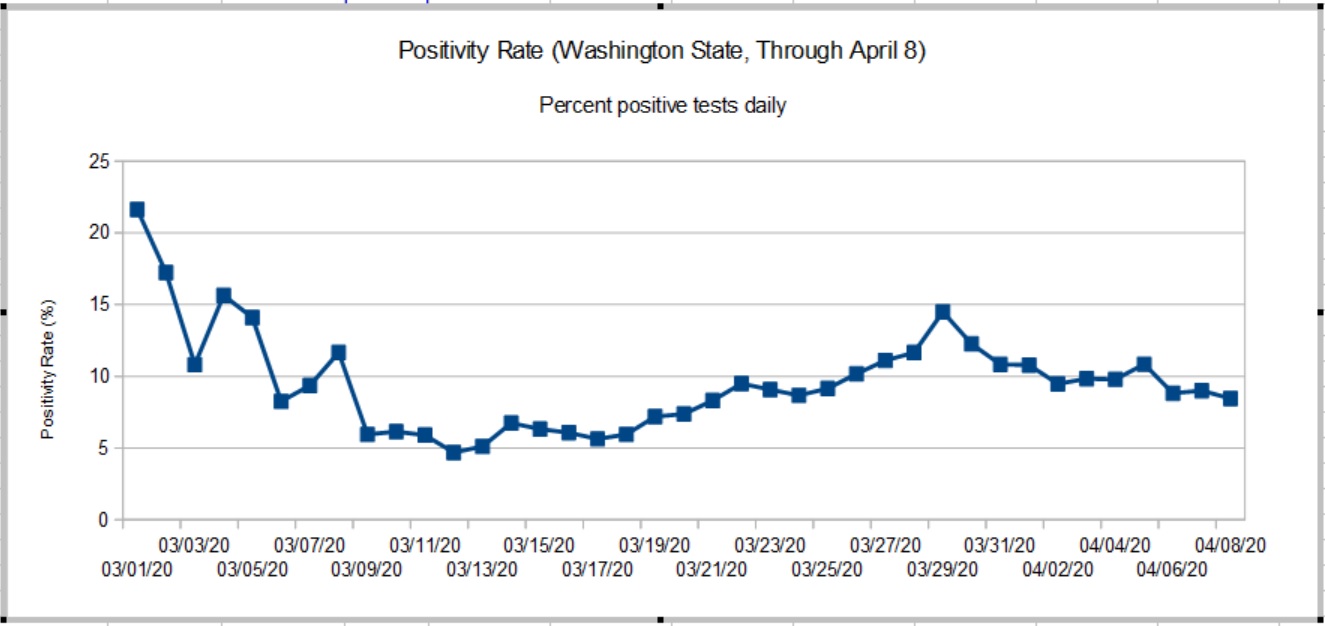
Because all test results for a given specimen day do not arrive at once, the DOH doesn’t guarantee complete results for the days just past. In keeping with their approach, my graph shows the Washington State positivity rate through April 8, 2020. [Click to enlarge graph.]
Washington State Positivity Rate (Through April 8, 2020)
The true peak in the rate occurred on March 28-29, 2020 when it hit 14.49%. The positivity rate has been slowly declining since then. The peak rate was more than double the 5% to 6% rate established around March 10. The new chart agrees reasonably well with raw statistics from the University of Washington Virology Laboratory. UW results, of course, are large portion of the State’s results. A back-of-the-envelope estimate shows that the rate has improved after April 8. Stay tuned.
So, what about those high rates in early March?
The positivity rate is a rather poor indicator which is subject to bias. COVID-19 tests are only administered under certain specific conditions because testing is rationed. Criteria include COVID-19 symptoms (fever, cough, tiredness, difficulty breathing) or contact with a known infected person. Properly, first responders may be given preference since they are most likely to come into contact with infectious people who may or may not be symptomatic. Further, COVID-19 hits nursing homes with vulnerable residents early and hard.
The general public has not been tested in a systematic epidemiological study, i.e., a random sampling of the population at large. Thus, the positivity rate as measured here is imperfect and may not accurately represent what the disease itself is doing in the overall community.
Contact is an important biasing factor and it is why I do not consider results in early March to be baseline. Public health authorities were actively pursuing contacts in early March after the first case of community spread was detected. The number of daily tests ranged from 74 to 500 — small numbers which are easily skewed.
As I’ve mentioned in earlier posts, today’s statistics tell us what the disease was doing 10 to 14 days ago due to the time required for incubation, development of symptoms, clinical presentation, and testing. Washington’s first community mitigation measures went into effect on March 11, with home-stay recommended on March 16 and home-stay ordered on March 16. I think we can safely say “Community mitigation works.”
Now we need the patience to finish the job and win the fight.
OK, that’s a little bit over the top. I was trying to find a way to work NPH into this post. 🙂
Viruses are the simplest biological forms. Viruses are obligate parasites. A virus must invade a host cell in order to reproduce. Viruses contain genetic material, but do not have ribosomes which replicate the genetic material. Viruses use ribosomes in the host cell for replication.
Since a virus cannot reproduce on its own, one may ask if a virus is alive. The question “What is life?” is non-trivial and is not as easy to answer as you may think. Another interesting question to consider is “How did viruses and life begin?”
Please note the term “genetic material.” Viruses are exceptionally diverse. Some viruses are DNA-based, some are RNA-based. Further, the genetic material may be single-stranded or double-stranded. On top of these characteristics, the material may have a linear or a circular structure, or be segmented or non-segmented. Amazing.
RNA-based retroviruses are a huge exception to Francis Crick’s central dogma: DNA makes RNA and RNA makes protein. In a retrovirus, reverse transcriptase (a chemical enzyme/catalyst) synthesizes a DNA copy from viral RNA. The DNA copy integrates into the host genome (in eukaryotic cells). Then, the cell’s protein and replication factory takes over. Eventually, the cell bursts or otherwise expunges the particles and a new cells are infected.
Both ribonucleic acid (RNA) and deoxyribonucleic acid (DNA) are large molecules (polymers) — chains of nucleic acid molecules. Genetic material (RNA or DNA) is rather fragile. Strong UV light or heat causes the chemical bonds in RNA and DNA to break. Whether it’s a cell or a virus, genetic material needs to be protected. A virus typically has a hard protein “shell”, called a “capsid,” that surrounds and protects the genetic material inside.
At this point, I recommend the NOVA Labs and Khan Academy tutorial about RNA before reading on. They do quite a decent job of describing RNA, transcription (copying), and protein synthesis. If you want to cut to the chase, jump to the Virus Wars section of the tutorial.
SARS-CoV-2
SARS-CoV-2 is the virus which causes COVID-19, the disease. It is a type of coronavirus. Calling SARS-CoV-2 “coronavirus” is really refering to this specific type of virus by a generic name. (Not quite correct semantically.)
Coronaviruses contain positive-stranded RNA. The RNA is surrounded by an envelope with spike glycoproteins on the envelope. Without a doubt, you’ve seen the SARS-CoV-2 protein model on television — a grey envelope with red spikes. The spikey glycoproteins are composed of two subunits (S1 and S2). The spikes assist binding to a host cell and injection.
SARS-CoV-2 protein model (CDC)
SARS-CoV-2 is approximately 60 to 140 nm in diameter. That’s darned small. A human hair has a diameter of 15 to 181 um, 1000 times larger. The bactrium E. coli is 1 to 2 um in length, still much larger than SARS-CoV-2. Viruses are exceptionally small; they must be small enough to invade host cells like E.coli.
SARS-CoV-2 has a single-stranded RNA genome. Its RNA strand contains 29891 nucleotides and encodes for 9860 amino acids. In biology-speak, that’s almost 30 kb (kilobases, not kilobytes). AS RNA-based viruses go, that’s a fairly large genome.
The Nucleocapsid gene (N), Envelope gene (E), Spike gene (S) and RNA-dependent RNA polymerase (RdRP) genes are important for testing. The WHO and CDC have developed nucleic acid amplification tests (NAAT) via reverse-transcription polymerase chain reaction (RT-PCR). Targeted genes include the N, E, S, and RdRP genes in the SARS-CoV-2 genome (WHO guidance). RT-PCR amplifies minute quantities of extracted SARS-CoV-2 RNA in a sample (if present) making it possible to assay one or more of the targeted subsequences (genes).
By now, you’ve come a long way along the journey and are ready for the summit. In closing, I recommend Features, Evaluation and Treatment Coronavirus (COVID-19) by Marco Cascella, et al. from the Istituto Nazionale Tumori – IRCCS – Fondazione Pascale. This paper is published by the National Center for Biotechnology Information (NCBI), a part of the U.S. National Institutes of Health (NIH).
If you would like to try your hand at sequencing, you can download the SARS-CoV-2 genome from NCBI. Don’t forget to snag a copy of BLAST. “BLAST finds regions of similarity between biological sequences. The program compares nucleotide or protein sequences to sequence databases and calculates the statistical significance.” STEM teachers, please take note of these resources. NCBI has many other genomes available for download.
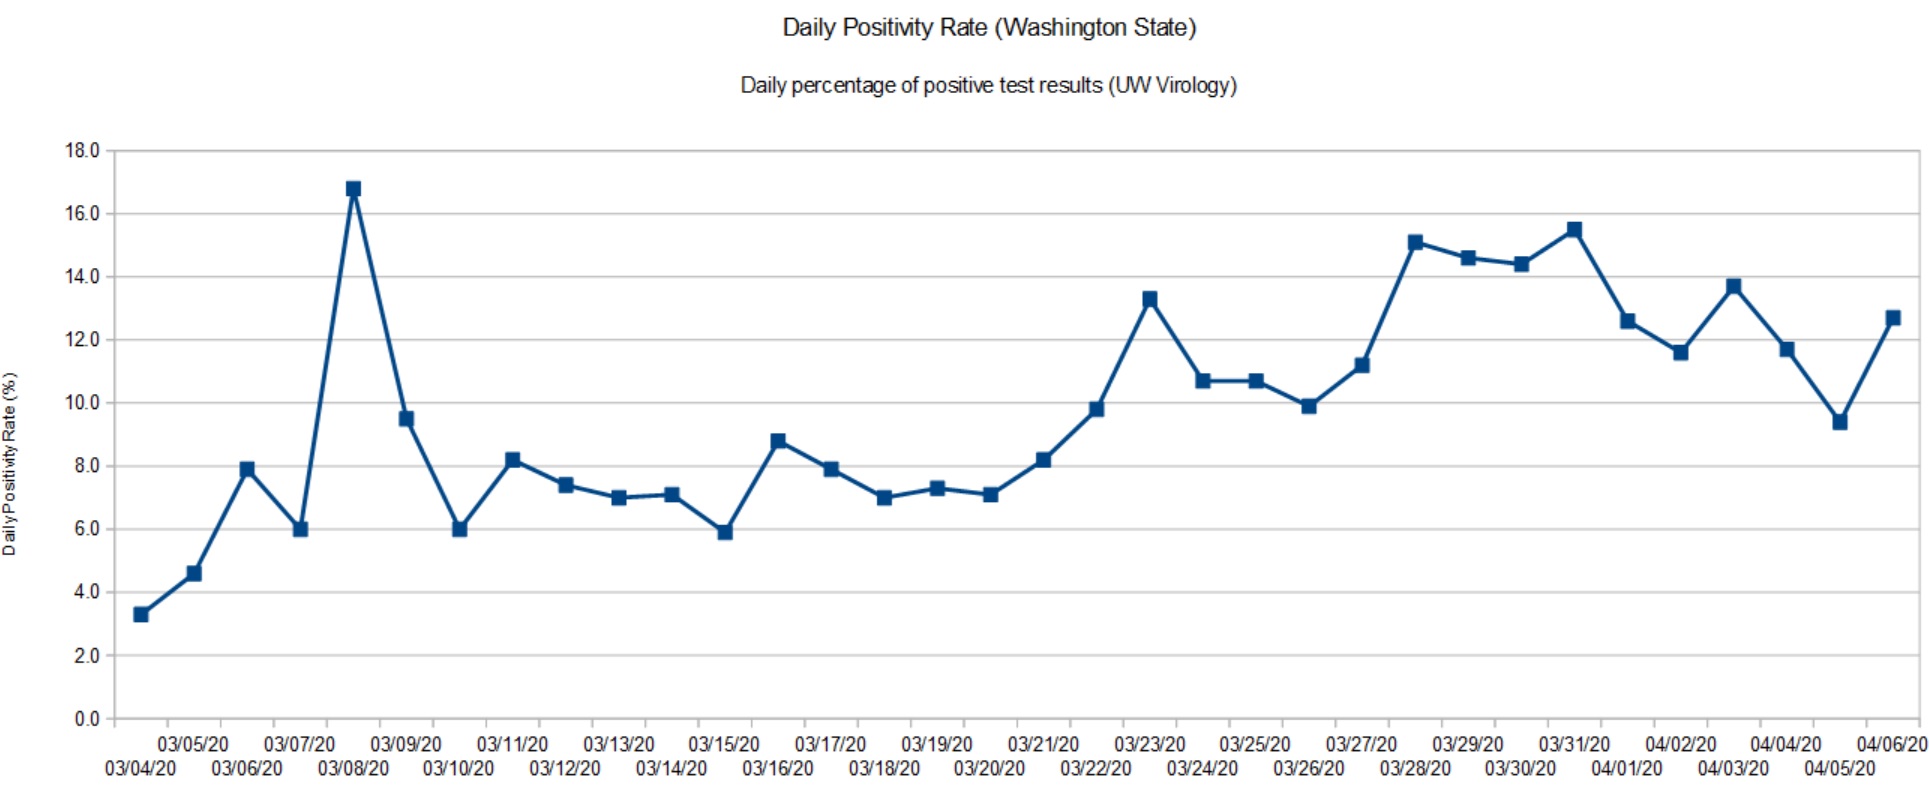
Another week has past and it’s time for new charts. I’ve been tracking the daily positivity rate for Washington State. The “positivity rate” is the percentage of positive test results for each 24 hour period. Dividing by the number of tests each day adjusts for variations in daily testing throughput, i.e., the number of tests performed each day is different.
Daily positivity rate (Washington State, April 3, 2020)
The gaps in the data are due to database issues at DOH. DOH receives and integrates test reports from around the state. Their database has been stressed and has not been tallying negative test results from which one can compute the number of tests per day (i.e., the sum of positive and negative results). Thus, I wasn’t able to compute a daily positivity rate for certain days.
Fortunately, I have the University of Washington Virology Laboratory as back-up. The UW Virology Lab is performing a large portion of tests in Washington. The Lab maintains a dashboard showing the number of tests they performed, the positives, negatives and inconclusives. Inconclusive tests are presumed positive. So, the daily positivity rate is the sum of the positive and inconclusive tests divided by the number of tests performed that day.
Daily positivity rate (UW Virology Lab, April 6, 2020)
Both graphs have a similar shape which shouldn’t be surprising as the UW Virology Lab is a major component in the DOH results. The positivity rate has more than doubled since early March. As of today (April 6), the positivity rate appears to be at a plateau and may show the beginning of a downturn. That’s good news and we need to remain committed to social distancing and other community mitigation measures.
Washington State recommended home-stay on March 16 and closed some businesses (e.g., hair salons, gyms, churches, etc.) I regard these measures as “social distancing lite.” On March 24, the State imposed a stay-at-home order. Given the time lag (10 to 14 days), the turn in the positivity rate is most likely due to the full stay-at-home order.
Fortunately, Governor Inslee has not declared victory. Instead, social distancing measures have been extended to May 4. Further, school has been cancelled through the end of the Spring term.
From my own observations, people in our part of Snohomish County (near Bothell and Everett) are treating COVID-19 seriously and are complying with the stay-at-home order. If a state, county or city is waiting for signs of an outbreak, don’t wait to issue a stay-at-home order. Response now will keep the size of your problem manageable. An ounce of prevention is worth a pound of cure.
Cleveland, OH
I keep an eye on the old hometown for no other reason than the Cavs and Browns. Cleveland.com published a few useful looking charts and graphs.
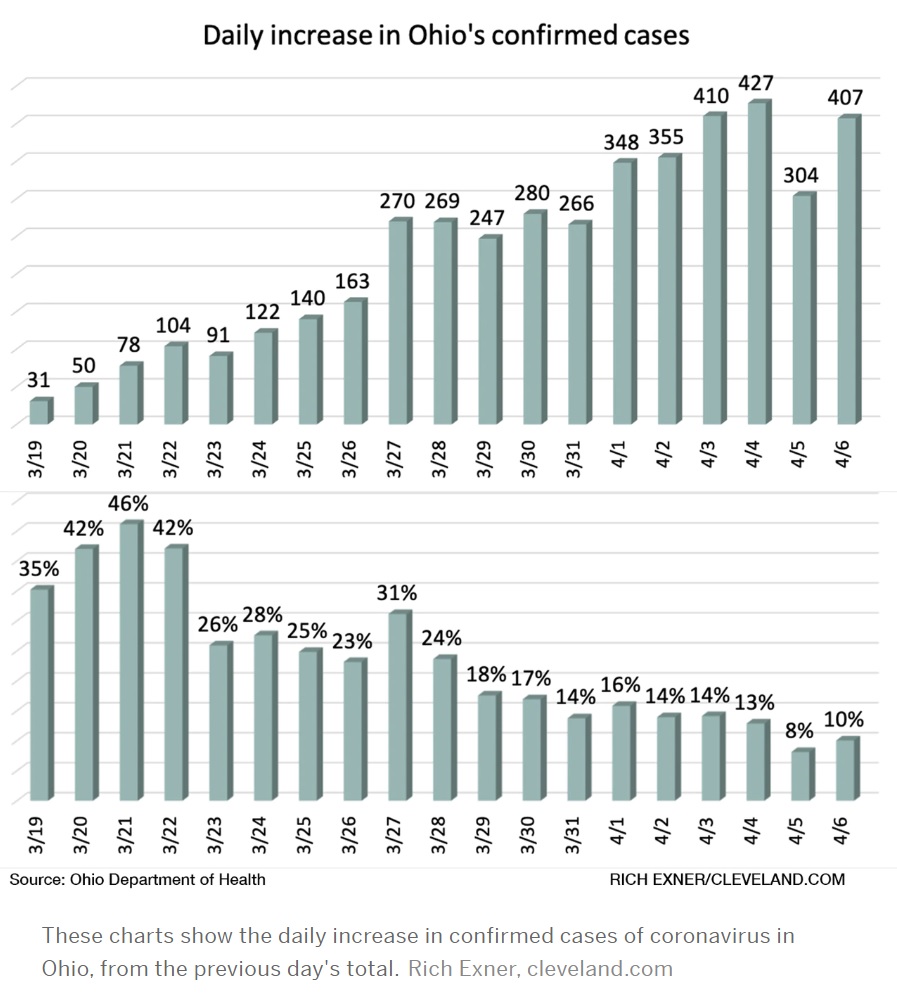
As we all go forward, we need to know when our communities have turned the corner and, importantly, when we can restart some business activities. The Ohio Department Health tracks the percentage increase in confirmed cases day-over-day.
Credit: Cleveland.com
Like Washington, Ohio has not hesitated to issue a stay-at-home order and to implement other forms of community mitigation. Gov. Mike DeWine, like Gov. Inslee, may not be the most dynamic individual, but he, too, is leading his state effectively in this crisis. I’m pulling for the folks at home!
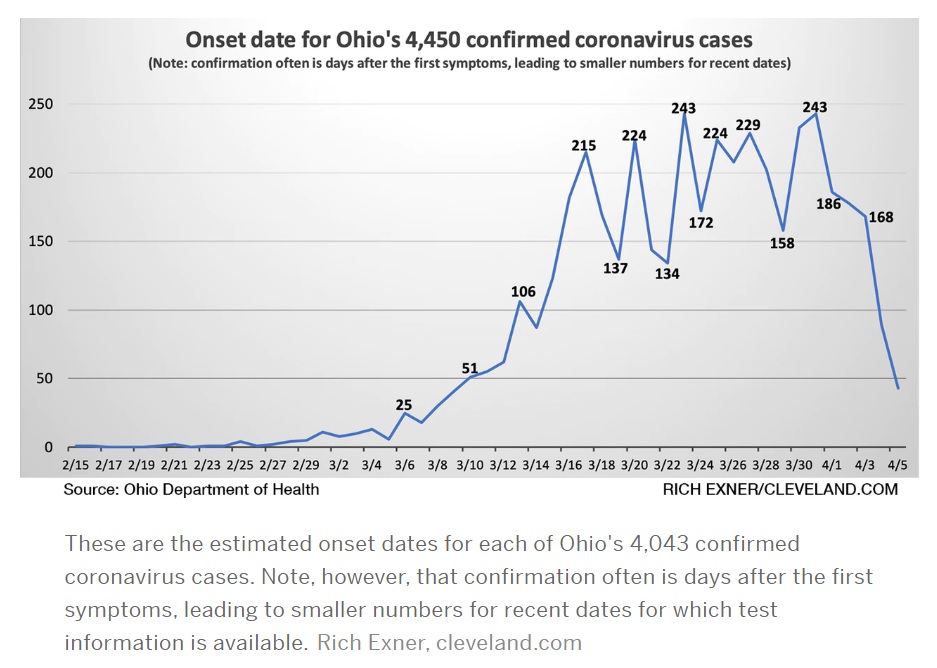
Credit: Cleveland.com
This is another Ohio DOH chart which caught my eye. It plots confirmed cases by the onset of symptoms. This chart better aligns case count with the actual time frame in which a patient was infected.
NYT: What’s next?
The New York Times published two good articles on community mitigation and the next phase in our battle against SAR-CoV-2 (COVID-19) — cycles of “suppress and lift” as restrictions are applied and relaxed, so-called waves.
Time for what’s known in the journalism biz as a “round-up.”
I started blogging about COVID-19 numeracy (AKA “by the numbers”) as a way to get my head around all of the data thrown at us by media outlets. Blogging also gave me a way to have the illusion of control over that which I cannot control, namely, the spread of COVID-19.
I hope that my blog posts are a resource for math and science teachers. (I try to keep these posts free of politics, BTW.) If there is a silver lining in all of this, what an opportune time to teach critical thinking and numeracy! I tried to collect the best and most useful examples of data presentation and, I collected a few stinkers, too.
So, here they are, links to my blog posts about COVID-19 numeracy:
If you’re a regular reader, you know that I usually deep-dive music technology and electronics. Fear not, I have been plugging away on music projects, too: Blokas MidiBoy, Toontrack EZKeys, recording demos with Genos, and more. All the projects for which I didn’t have time. Guess I’ve got the time now, just like everyone else. 🙂
I hope to blog about music-related topics as I’m not sure how much value I can add to the on-going COVID-19 discussion. I will continue to track the positivity rate for Washington State since this is my home with family and friends nearby. Plus, there are always subjects (e.g., reverse transcription polymerase chain reaction/RT-PCR testing) that pique my scientific interest.
Washington Post: Bending the curve
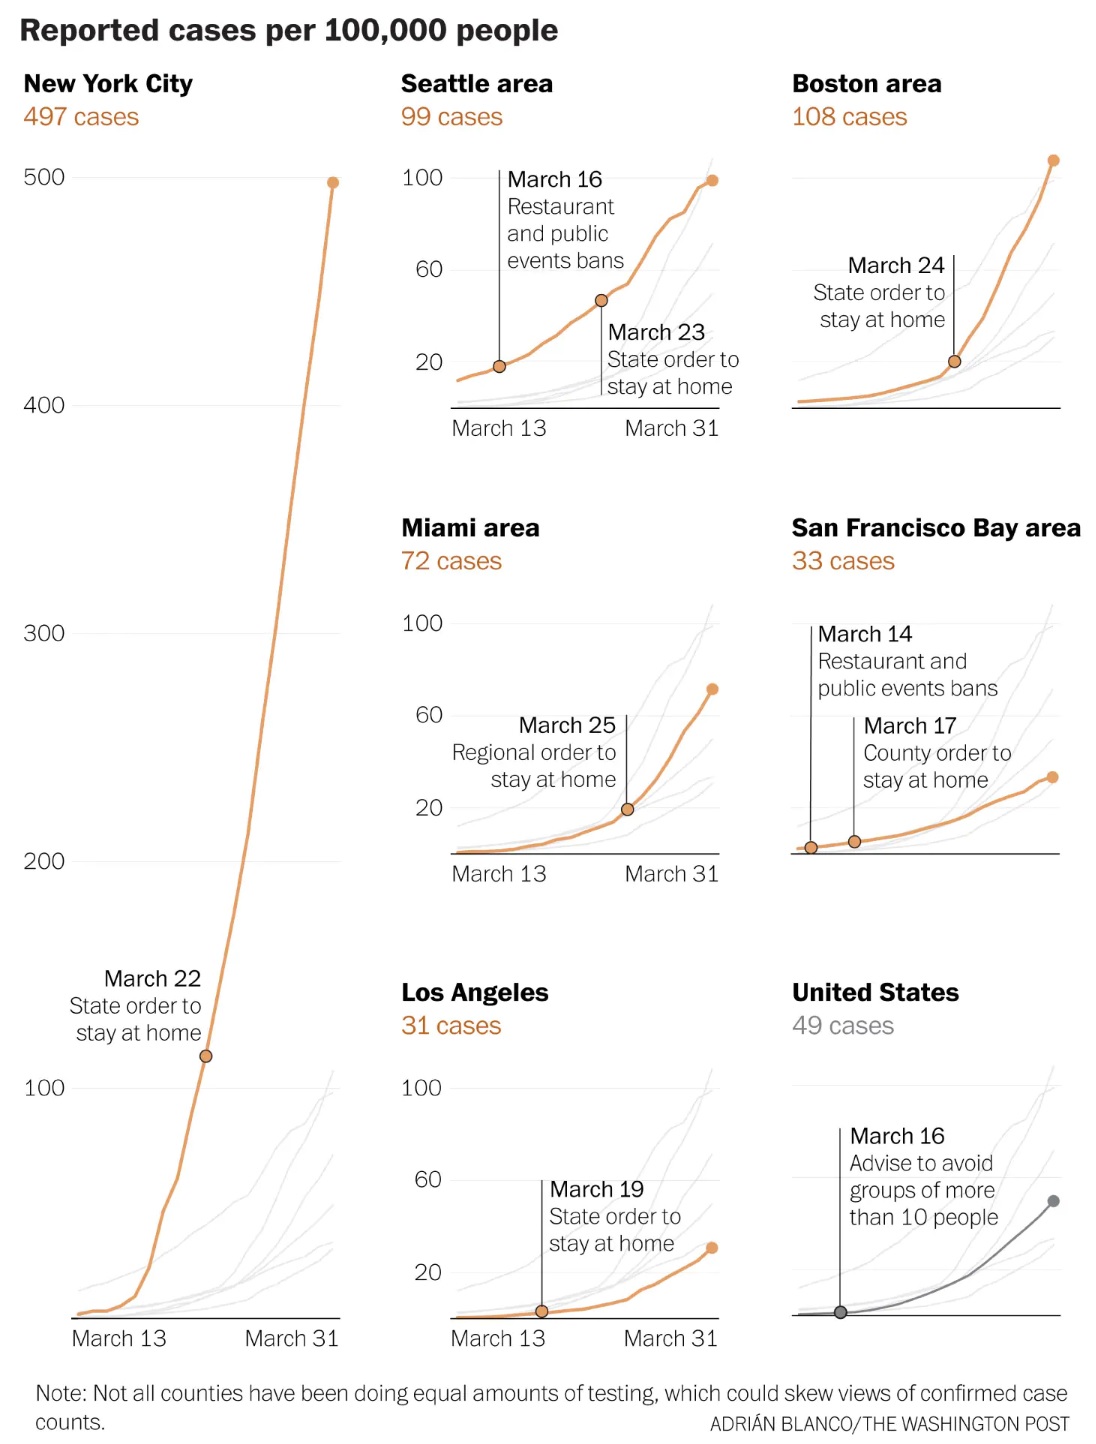
Here’s a quick hit from the Washington Post. It’s a set of graphs illustrating the effect of social distancing for select U.S. cities.
Source: Washington Post (April 2, 2020)
With respect to Washington State (Seattle), it’s still early days, really. I think my original guidance holds — we won’t really see a bend from another 7 to 14 days out from this point (April 2). Washington State imposed its first social distancing on March 16 followed by a stay-at-home order on March 23. With the delay due to SARS-CoV-2 incubation, development of symptoms, clinical presentation and testing (10 to 14 days according to medical experts), we should just now be seeing a bend in the curve.
The Washington State Department of Health (WADOH) has had technical issues with its disease reporting database. The original database could not handle the incoming stream of reports including negative test reports. So, the WADOH database went dark for a few days recently and is just now coming back. Due to these technical glitches, we need a little extra time to see the effect of social distancing in Washington.
Stay apart and keep all of us healthy — P.J. Drongowski
A New York Times article (March 29) suggests that social distancing is beginning to pay off in the Seattle area. The NYT article refers to work performed at the Institute for Disease Modeling in Bellevue, WA. The authors are cautious saying that data is preliminary and unpublished.
Quoting the IDM web site:
IDM shapes global efforts to eradicate infectious diseases and to achieve permanent improvements in the health of those most in need. By developing, using, and freely sharing computational modeling tools, we advise policymakers, promote quantitative decision-making and advance scientific methodologies.
IDM is an institute within the Global Good Fund, a collaboration between Intellectual Ventures and Bill and Melinda Gates.
Currently, IDM is working on disease transmission dynamics for malaria, polio, tuberculosis, HIV, pneumonia, typhoid, and more.
Personal thanks to Bill and Melinda Gates for their philanthropic work.
IDM published a report (as of March 29) on the effects of social distancing and mobility reductions on COVID-19 in King County, WA. Quoting the report:
Still, based on this data for King County, the trend clearly shows Re decreasing from about 2.7 in late February to roughly 1.4 on March 18th. These estimates come with high uncertainty, and while the trend is encouraging, it remains unlikely that COVID transmission in King County was below the 1.0 threshold on the 18th.
[We] cannot say with confidence if Re is below or above the critical threshold of 1 today.
Re is the effective reproductive number for COVID-19.
Thank goodness, Governor Inslee is not declaring victory either. Community mitigation measures remain in place and likely will be extended. (The federal guideline is currently April 30.) In his interview on CNN’s “State of the Union” on Sunday, the Governor cited shortfalls in testing supplies (swabs, vials, etc.) which are limiting the number of tests performed daily. As I’ve said before, we need community-wide epidemiological studies to get ahead of the disease. We cannot perform epidemiological tests (surveillance testing) when we can barely perform diagnostic testing for symptomatic patients.
The Fine Print
Let’s get nerdy. How do IDM define R0 and Re. Quoting the IDM glossary:
R0 (R Naught, Basic reproductive number): The average number of secondary cases a typical infectious individual will generate without any interventions in place to reduce transmission. The number of secondary cases per source is expected to change over time and space with different interventions and as the proportion of the population with immunity grows (REff).
REff (R Effective) or Re: The number of secondary cases each infectious individual will generate, on average, after interventions are in place and/or part of the population is immune. We would expect REff to be less than R0.
Washington Department of Health
The Washington State Department of Health upgraded COVID-19 reporting on their web site. They are publishing better graphs and data, especially data about testing. I’d like to see graphs for the posivity rate over time since the ratio of daily positive tests divided by the daily number of tests adjusts for day-to-day variations in testing. (“Daily” means for each 24 hour period.)
Positivity Rate
Governor Inslee referred to this ratio as the “Positivity Rate” and I like that term. It’s more concise than “Percentage of positive tests per day.”
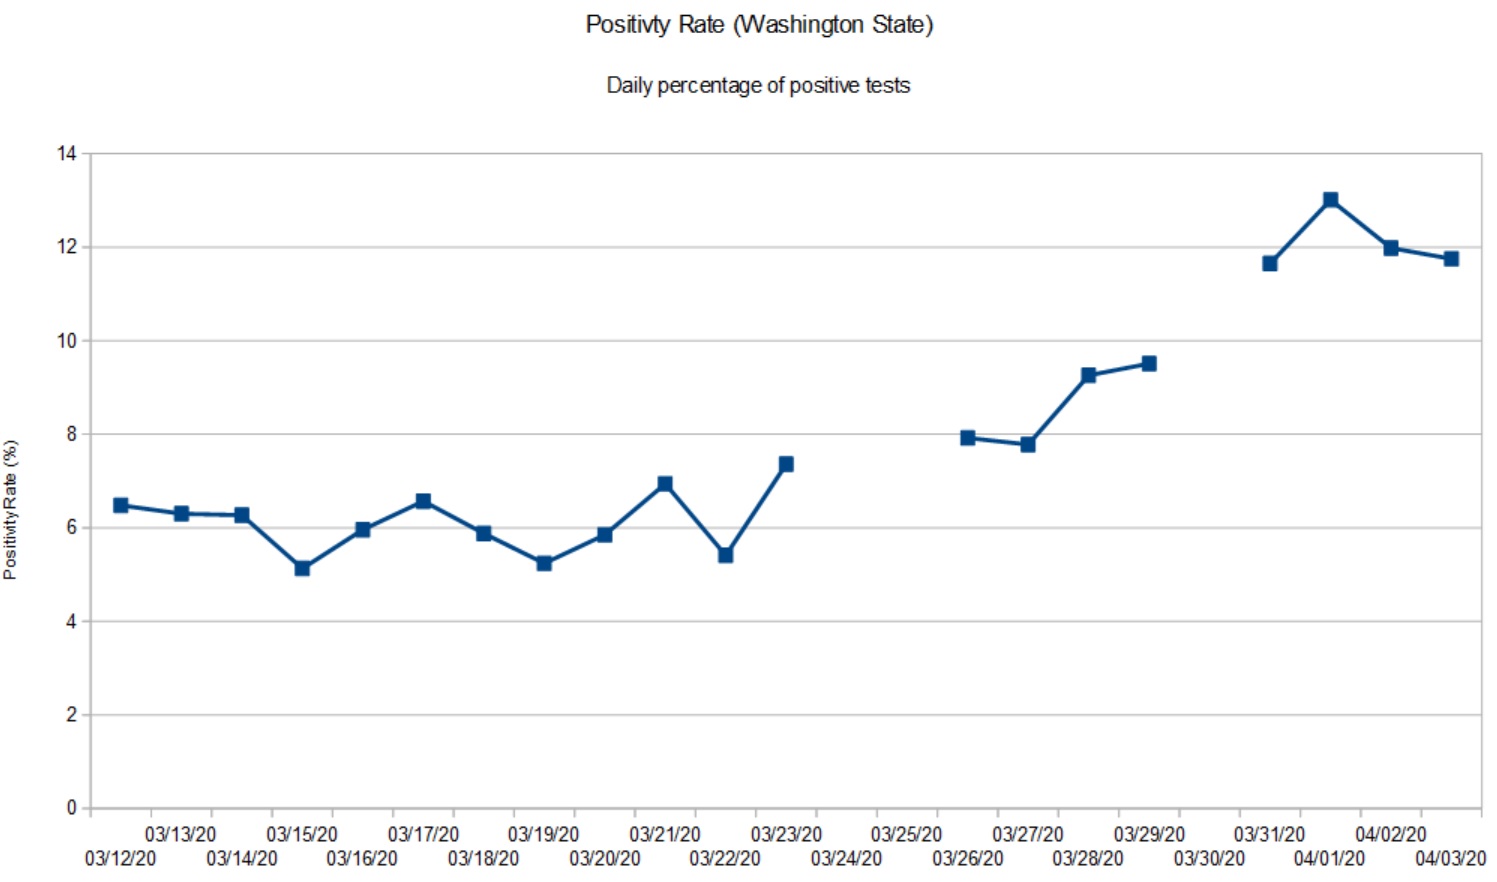
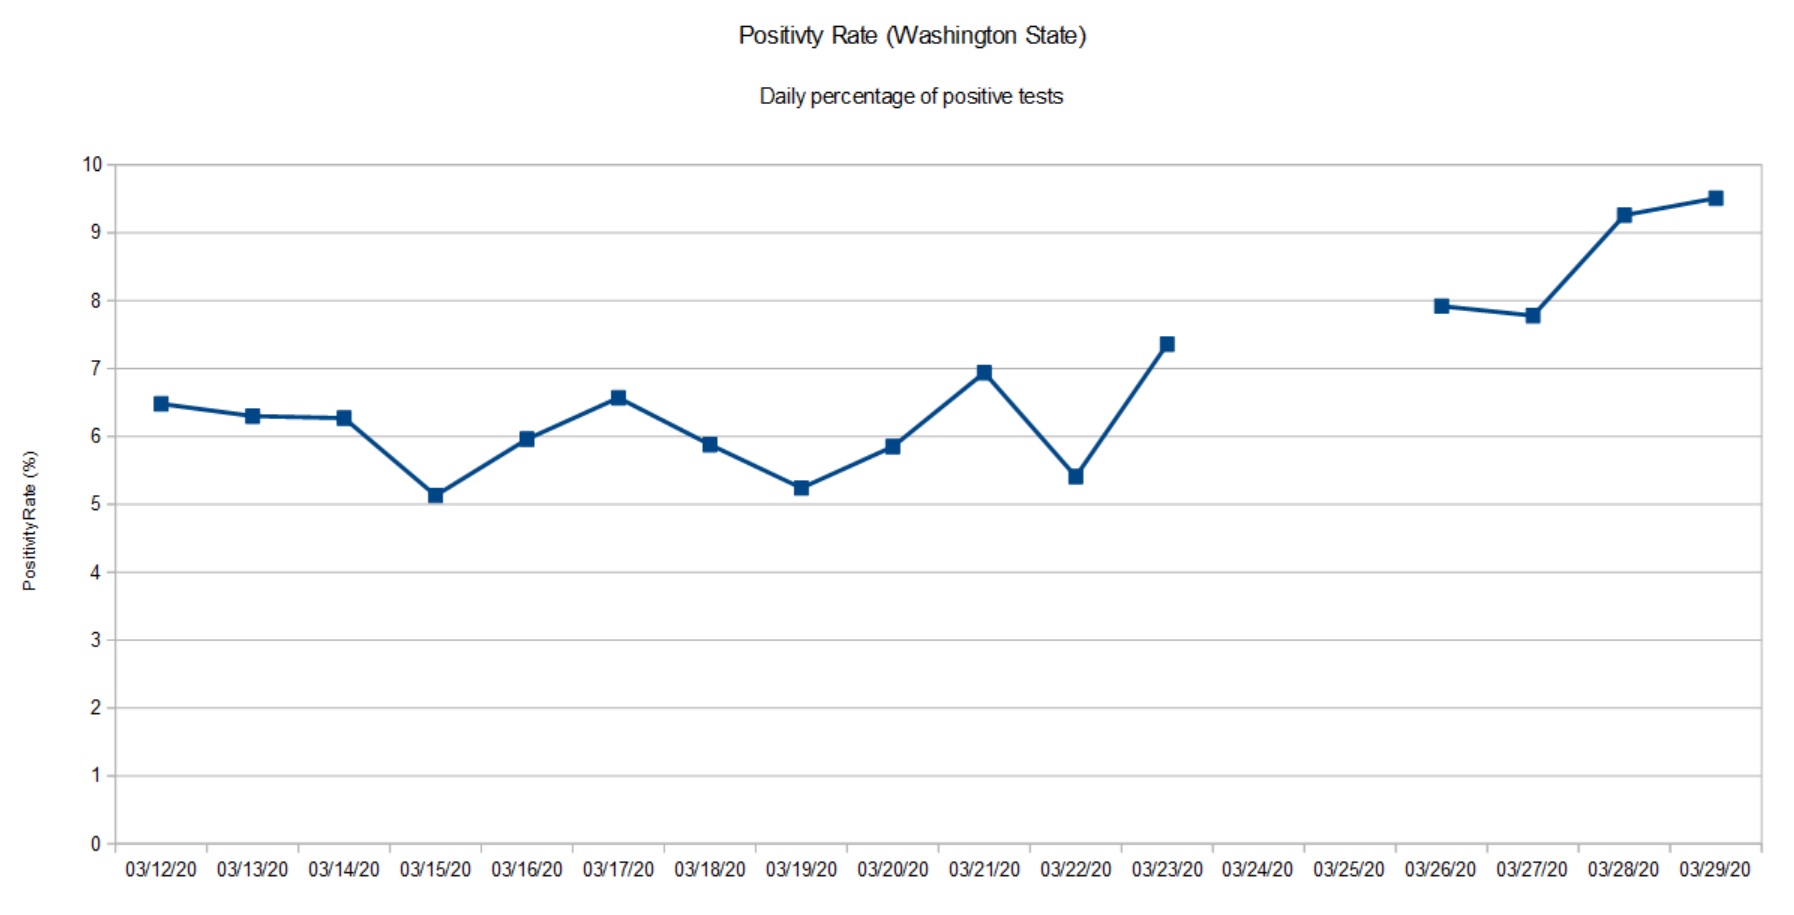
Below is my plot of the Washington State positivity rate starting March 12 to March 29. Although the press is optimistic, The positivity rate has doubled over the time period. [Click image to enlarge.]
Washington State Positivity Rate (March 12 to March 29)
The gap in the graph is due to missing data from the Washington State Department of Health. They ran into database glitches March 24 and 25. The March 26 data point aggregates positive cases and tests across the gap.
There are several factors that affect the positivity rate. First off, this is not a random sample of the population at large. People are tested only if they satisfy a protocol, that is, satisfy a set of criteria. Criteria include presence of COVID-19 symptoms (fever, cough, shortness of breath), contact with a known infected COVID-19 patient, or in-coming travel from a known COVID-19 hot-spot (e.g., China, Italy, New York City metro, etc.) No doubt, some of the tests are due to contact tracing as officials try to identify possible carriers in order to isolate them. Bottom line, the positivity rate is far from a controlled epidemiological study (surveillance).
Please remember that any measurements we take today show what the virus (SARS-CoV-2) was doing 10 to 14 days ago. The delay is due to incubation, development of symptoms, clinical presentation and testing.
At this point in time (March 30), I’m glad that Washington State is staying the course and is looking at additional restrictions.
BTW, I’m still trying to absorb the changes to the Washington State Department of Health site. Their graphs don’t always jibe with my table of previously published data.
At the beginning of March, The Skagit Valley Chorale discussed weekly rehearsals and whether they should go ahead. Skagit County had not yet reported any cases of COVID-19. On March 6, they decided to go ahead with rehearsal on March 10. The chorale members used hand sanitizer and minimized contact during rehearsal.
None of those precautions, however, prevented an outbreak. Three weeks later, 45 members have been diagnosed with COVID-19 or have had symptoms. At least three members were hospitalized and two are dead.
Fortunately, our own church group passed on rehearsal during the same time frame.
This tale should be a warning to any community that feels safe because they have not yet experienced the disease. Please pay attention to our public health officials who predict eventual outbreak everywhere. Start social distancing and isolation now.
    Car crash fatalities (2019)    38,800 people
    Vietnam War fatal casualties   58,220 people
    Hiroshima fatal casualties     90,000 to 146,000 people
    Nagasaki fatal casualties      39,000 to 80,000 people
    COVID-19                       ?
Yesterday, CNN carried interviews with Dr. Anthony Fauci and Bill Gates. Both gentlemen called for community-wide epidemiological studies of COVID-19. We need to know the prevelance of the disease in our communities in order to assess the effectiveness of community mitigation (i.e., social distancing).
Broadly speaking, there are two kinds of COVID-19 testing:
Diagnostic testing
Epidemiologic testing
Diagnostic testing is patient-focused. It determines if the tested individual is infected with SARS-CoV-2 (the virus which causes disease COVID-19) in order to isolate and treat the patient. Due to limited test capacity, all testing to date is diagnostic in purpose.
There are variants of diagnostic testing on the horizon such as a test to determine if an individual has acquired immunity to COVID-19 or not (antibody testing).
Epidemiologic testing is like a political poll. People are selected at random from the community, statistically called the “population.” The selected people are tested for SARS-CoV-2 infection using the same kind of medical test employed in diagnostic testing. Personal information is also collected such as age, sex, presence of underlying medical conditions, previous COVID-19 diagnosis, and so forth. Statistics are tallied and summarized such as the percentage infected, susceptible (not yet infected) and immunity. Like a political poll, the statistics are broken out by age, sex and so forth.
We have not yet performed a single community-wide epidemiological study of COVID-19. This leaves us blind to one important segment in the community — people in the community who are infected and are asymptomatic. We know that asymptomatic people are a significant factor in the spread of SARS-CoV-2 and COVID-19.
Impatient people are already chomping at the bit to restart the American economy. Given that we are only 2 weeks (at best) into community mitigation, this is preposterous. [Some communities have not even started social distancing and they are late.] At some point, though, we must restart the economy. Epidemiological studies will help us to decide if it is safe to reduce community mitigation and allow the free flow of commerce again.
One important factor in the decision to reduce mitigration is the degree of immunity in the community, the so-called “herd immunity.” The community (the herd) becomes protected from a disease when a large portion of the population (typically, 60%) is immune to infection. Infected individuals often become immune when they successfully fight off and recover from the disease (acquired immunity). Better yet, individuals can be made immune through vaccination.
Acquired COVID-19 immunity has not been confirmed by scientific study at this time. Based on prior experience with other coronaviruses, medical experts believe that recovered individuals will be immune to SARS-CoV-2.
“Flattening the curve” has two benefits. First, it reduces the strain on the health care system (hospitals, doctors, nurses and other caregivers). Second, it buys us the necessary time to develop a safe vaccine and to get a vaccination program ramped up and put in place. In some sense, developing the vaccine is the easy part. The time-consuming part is the medical trials and studies needed to assume safety and efficacy.
The Seattle Flu Study was initially started to detect, monitor and control influenza outbreaks in Seattle using rapid virus genetic sequencing and mapping chains of transmission. The study is led by the Brotman Baty Institute, in collaboration with UW Medicine, The Fred Hutchinson Cancer Research Center, and Seattle Children’s.
With the outbreak of COVID-19, the Seattle Flu Study was “repurposed” to COVID-19. Quoting:
To track the spread of COVID-19, SCAN will collect nasal swabs from a sample of people across Seattle and King County, working to mirror the area’s population as closely as possible. We’ll collect swabs from both those who are healthy and those who feel sick and will also test de-identified clinical residual samples (these are left-over samples from tests performed for other reasons at clinical laboratories). The results of these tests will help us understand the outbreak more completely and, along with other data sources, help inform public health decisions. SCAN is not able to offer testing to every individual but the whole community will benefit from the program.
I look forward to the results of the SCAN study since we live a stone’s throw away from King County, Washington. This is our ‘hood.
Logarithmic graphs
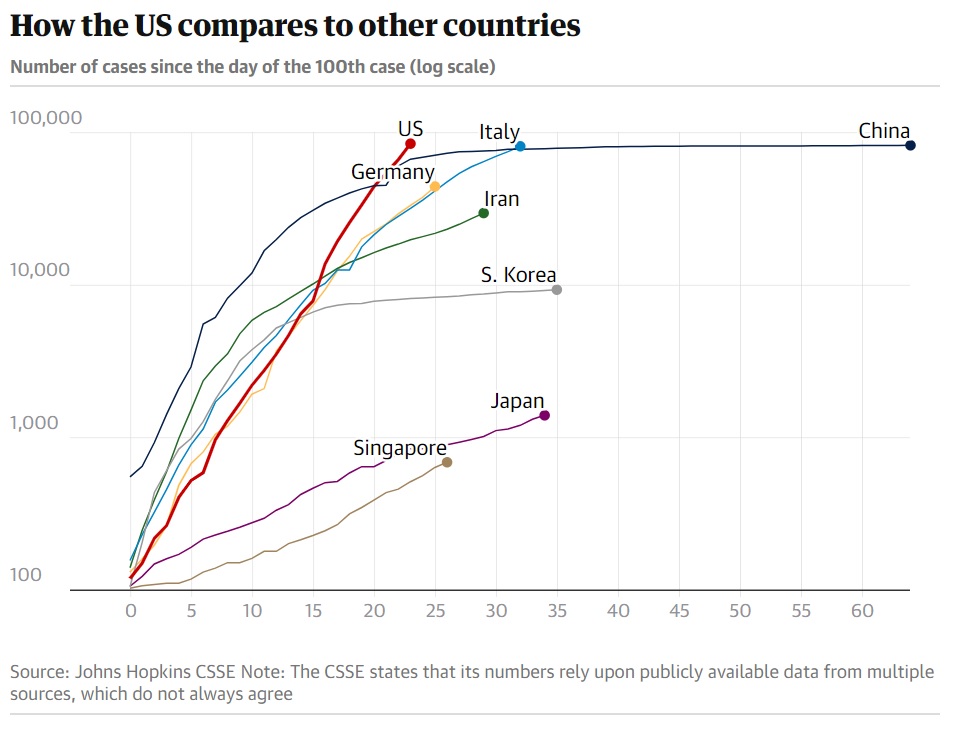
Logarithmic graphs are good tools when analyzing phenomena with exponential growth. At this point, we’ve all seen linear scale graphs showing the steep rise of COVID-19 cases. Each tick in a linear scale graph has the same statistical weight, e.g., 100, 200, 300, 400, etc.
A logarithmic graph has a logarithmic scale. Each tick increases by a power of 10, e.g., 100, 1,000, 10,000, 100,000, etc. An exponential trend appears as a straight line in a logarithmic graph. Here is a logarithmic graph (from The Guardian, March 27).
Source: The Guardian (March 27)
Sadly, the United States is on an exponential trajectory. China and South Korea, in particular, have asymptotic curves, showing successul COVID-19 community mitigation. Those two countries are “flattening the curve.”
New York State Hospitalizations
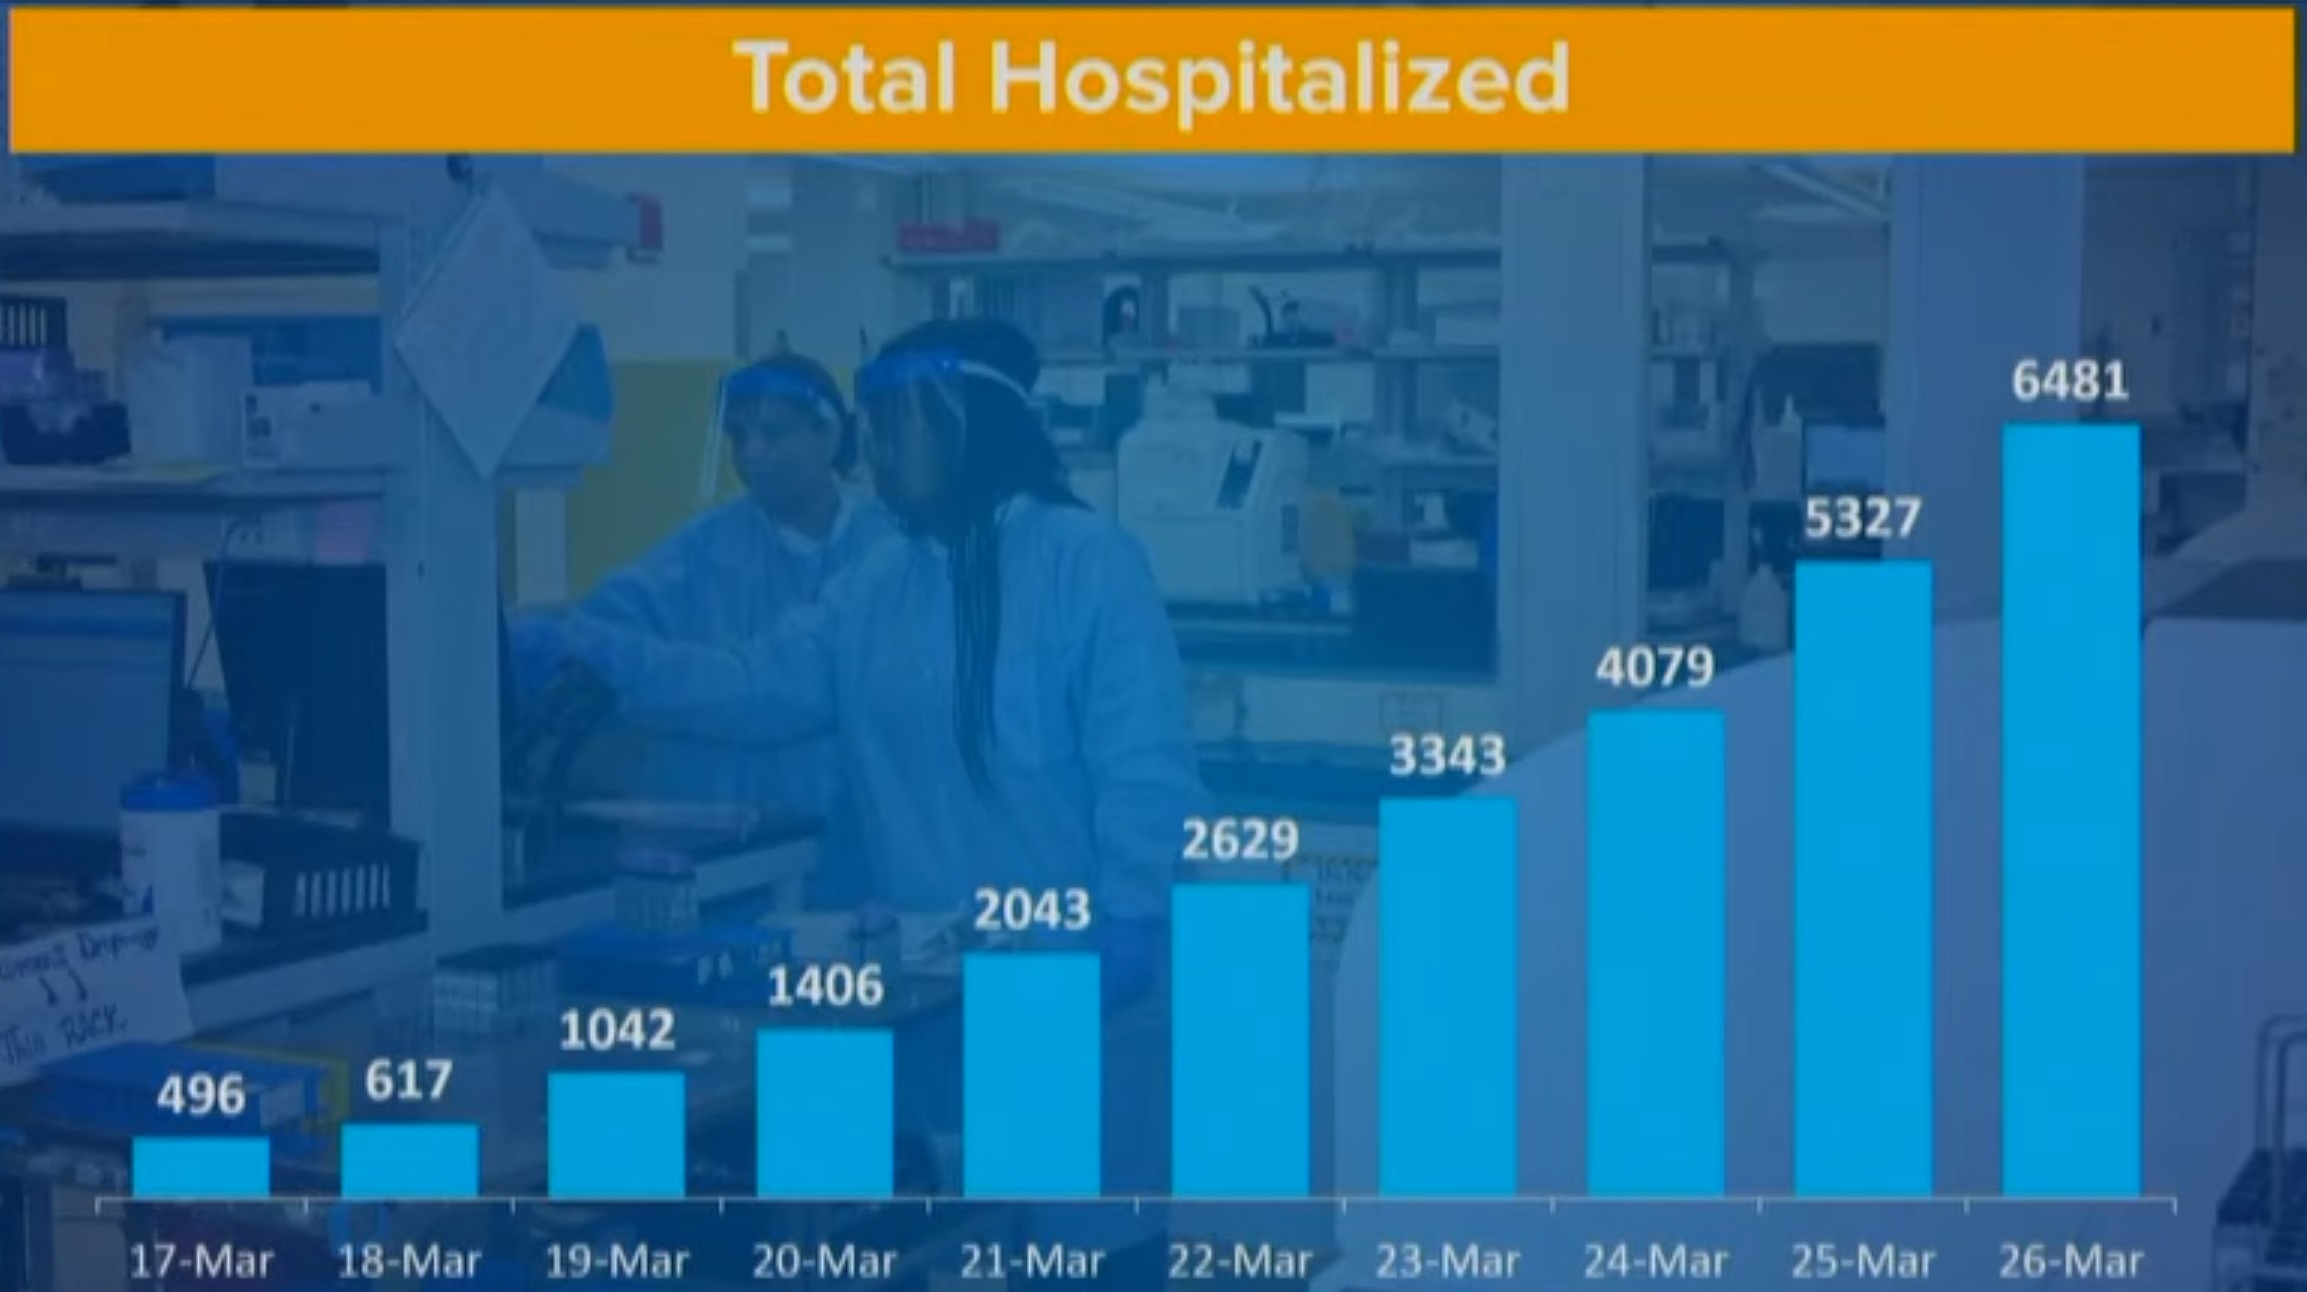
Gov. Andrew Cuomo of New York presented an important and useful graph during his briefing this morning.
New York State COVID-19 Hospitalizations Through March 26
This chart shows the number of hospitalizations per day. Please note that the number of hospitalizations is increasing by almost 1,200 new patients per day. No health care system can sustain this kind of growth. New York State expects the apex of hospitalizations in 21 days, adding a further 25,200 hospitalized patients, if the current rate continues.
As I mentioned earlier today, The New York Times staff has published some excellent maps, charts and interactive simulations.
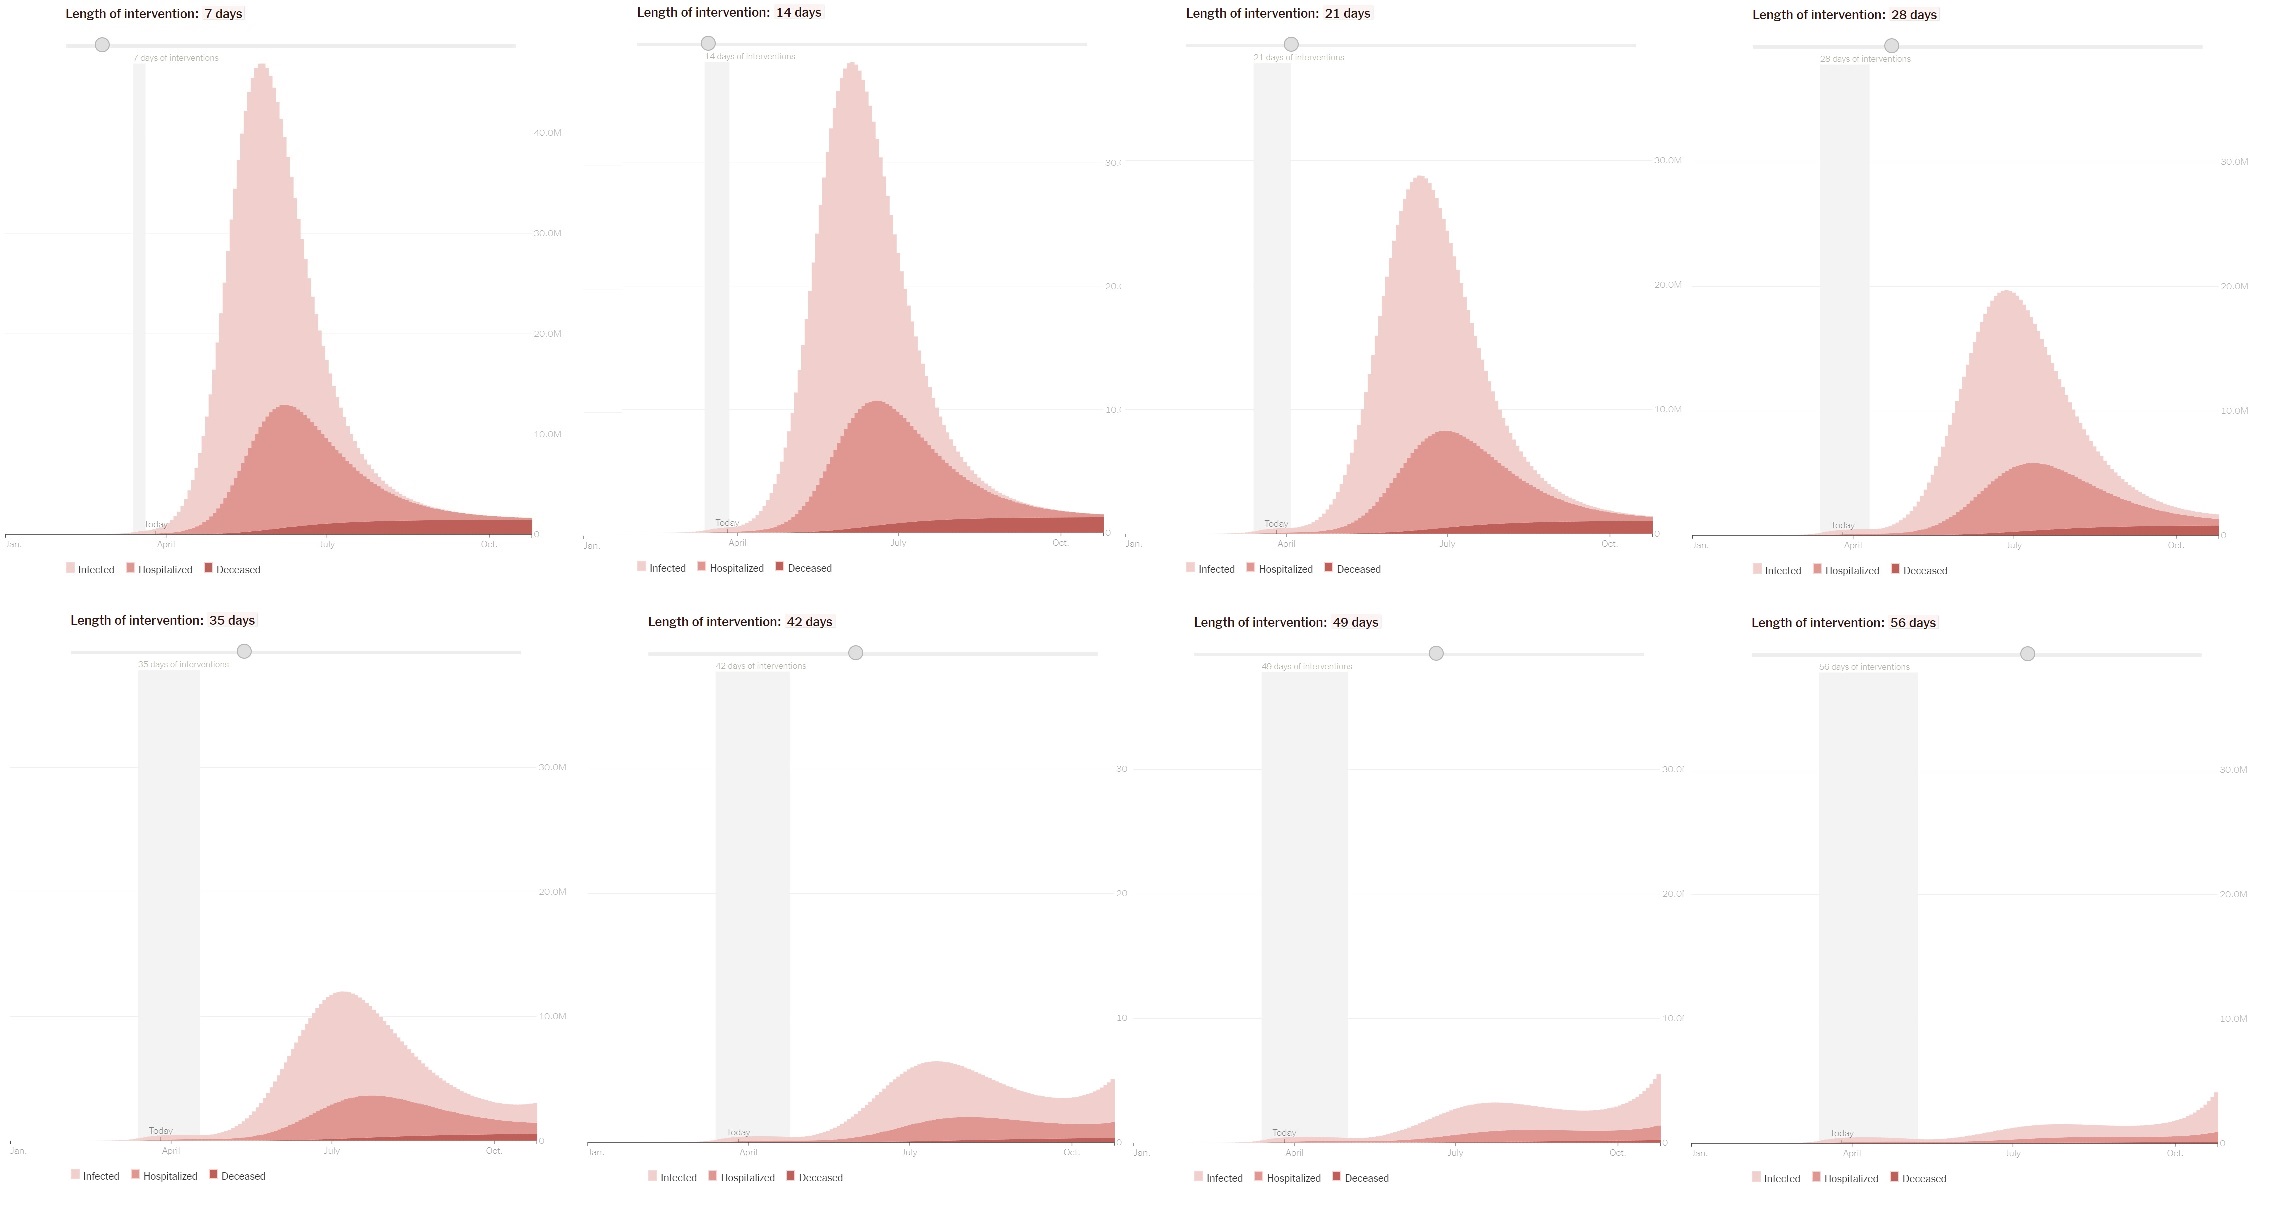
Their latest interactive simulation illustrates the effect of community mitigation (i.e., social distancing) for varying periods of time. I took snapshots at weekly intervals (social distancing for 7 days, 14 days, 21 days, etc.) [Click to enlarge.]
Effect of community mitigation for different time periods (NYT)
The curve in the lightest shade is the number of infected people. The middle shade curve is the number of people hospitalized and the darkest shade curve is the number of deaths. Each tick in the vertical scale is 10 million. Yes, millions. I recommend reading the article itself for assumptions and caveats on the mathematical model.
From this time series, it’s easy to see that two weeks (14 days) of community mitigation is wholly inadequate for suppressing the disease, let alone stopping it. To my eye, the shortest reasonable duration is 42 days (6 weeks).
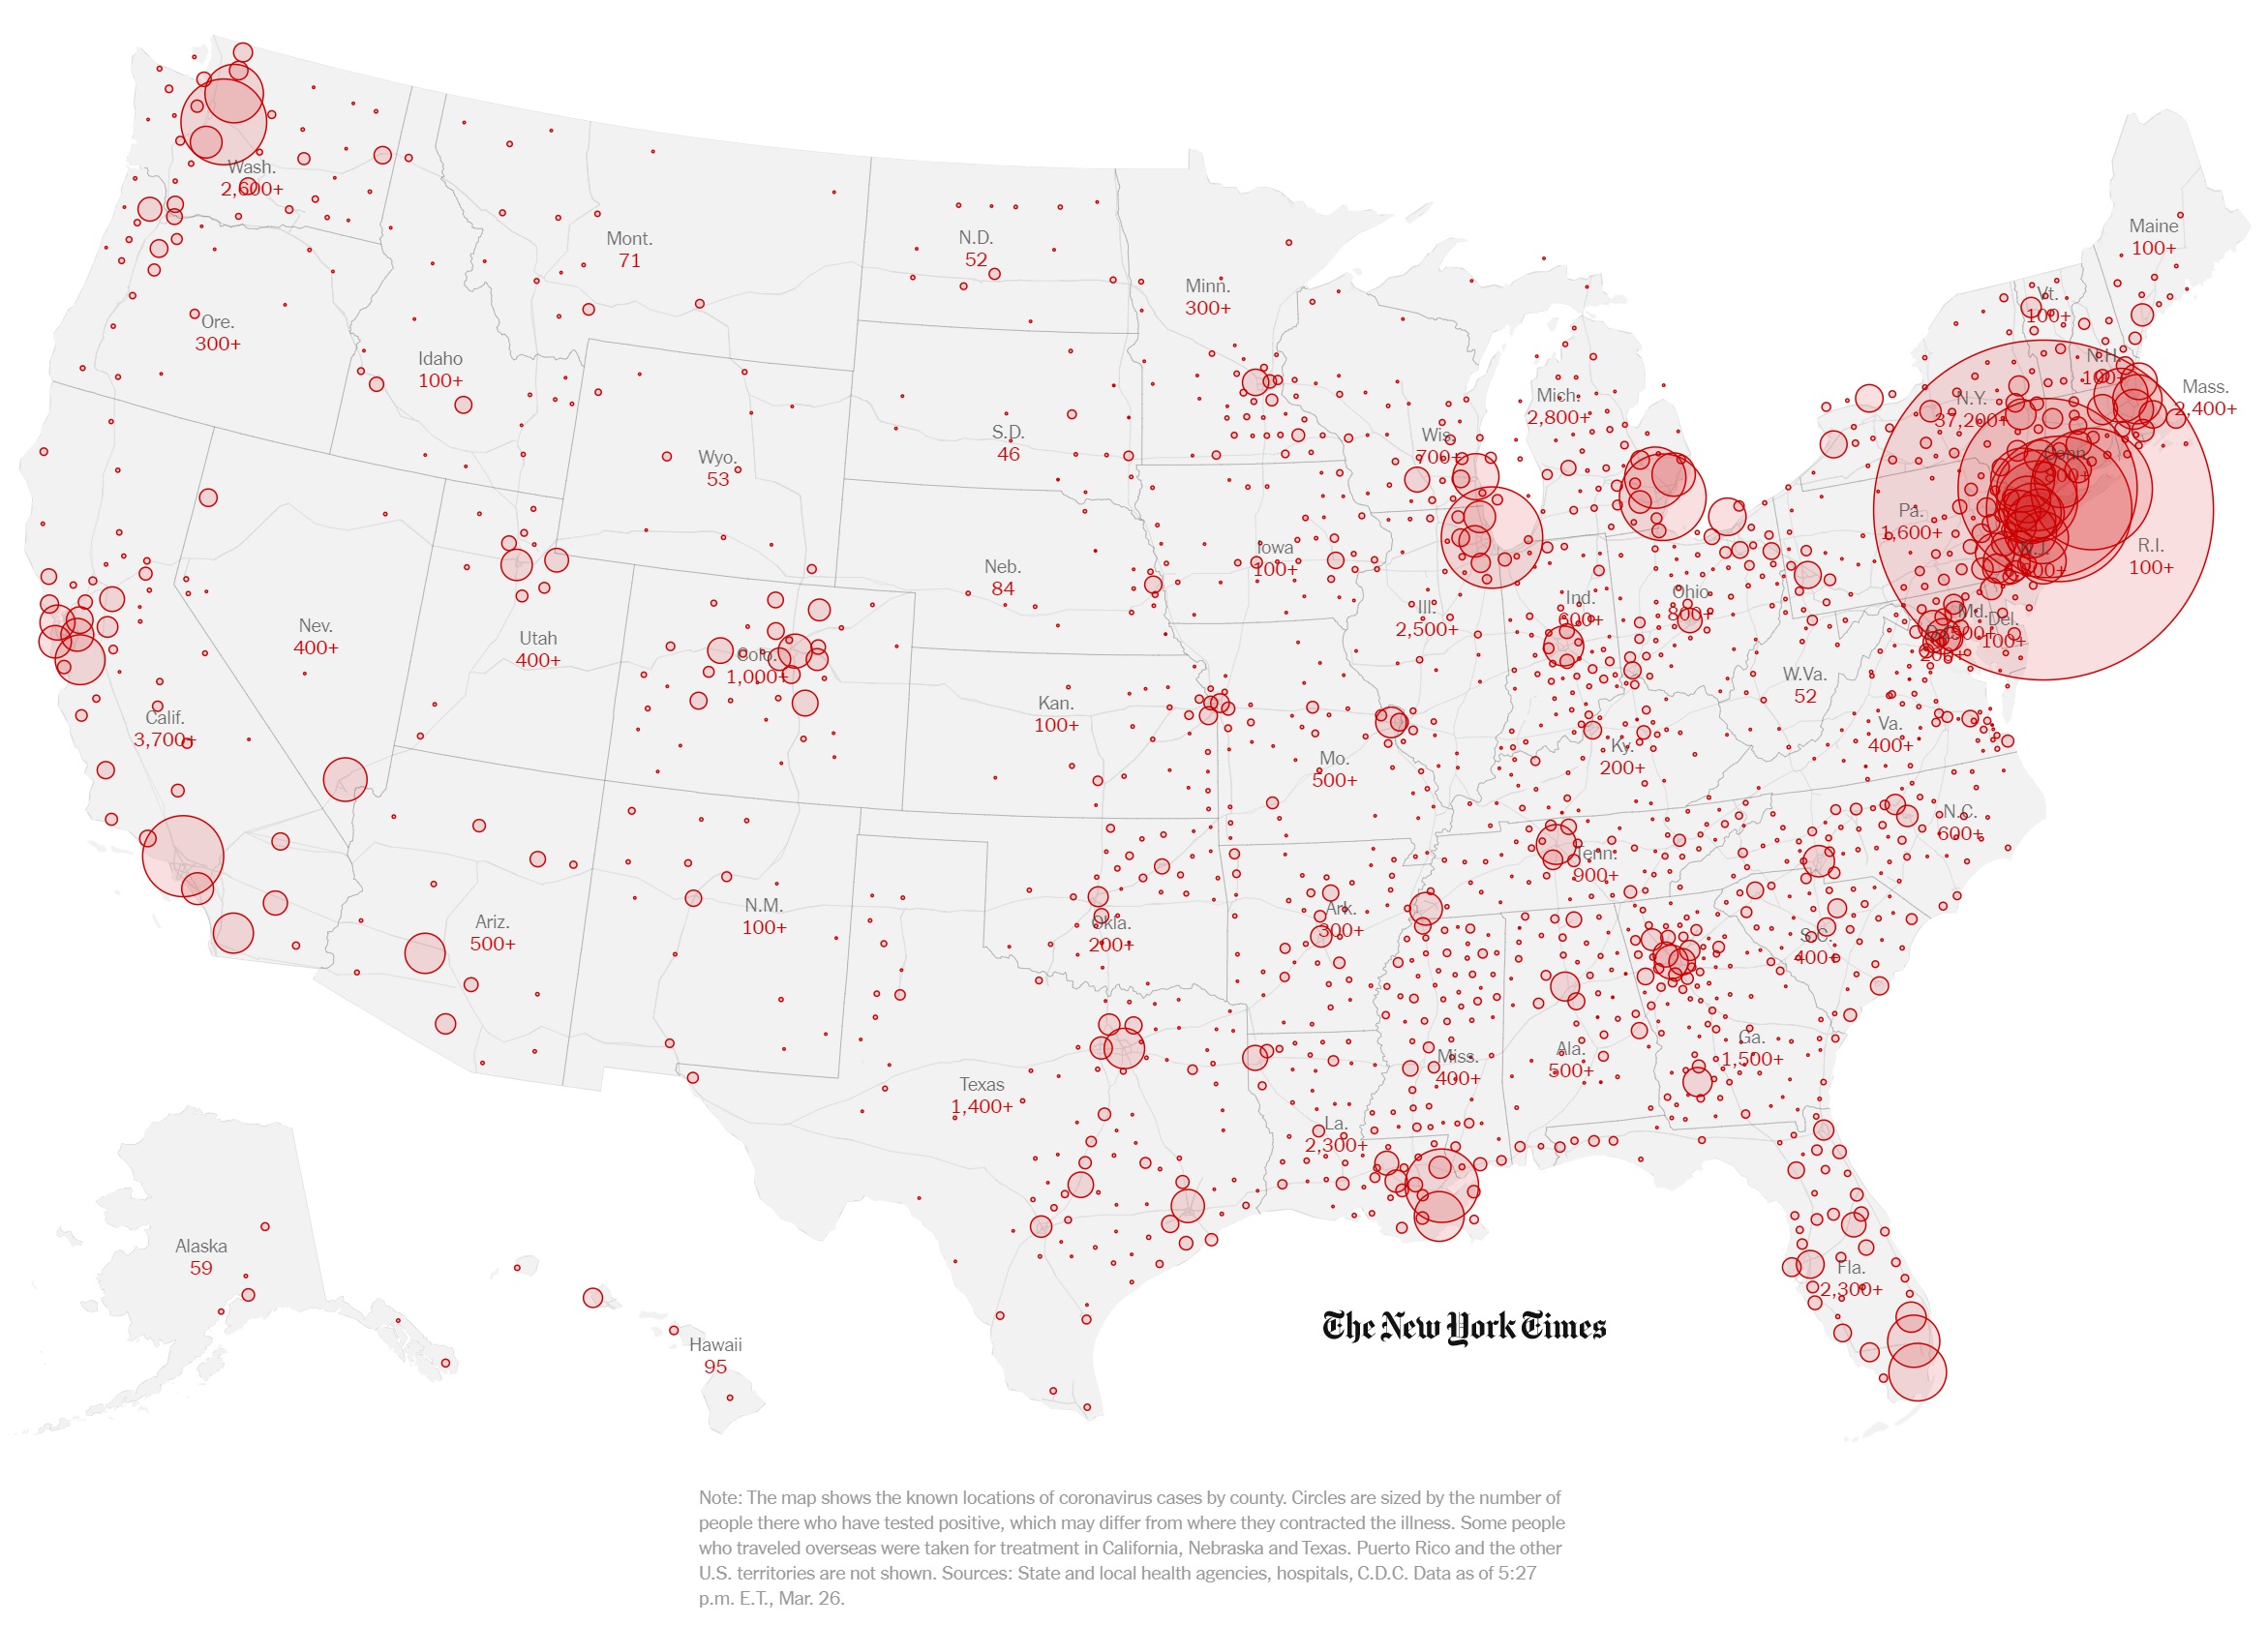
Here is the latest NYT map (March 26, 2020) depicting the spread of COVID-19 across the United States. [Click to enlarge.]
Spread of COVID-19 (The New York Times, March 26, 2020)
Dedicated to Edward Tufte, who is still kicking around, thank goodness.
Governor Cuomo, in his briefing today, asked why New York State is leading the United States in positive COVID-19 cases. Let’s compare the top four states:
                     Total   Total   Percent
    State            Tests   Cases  Positive  Date
    -------------   ------  ------  --------  ----
    New York        38,390  14,904     38.8%  3/24
    Massachusetts   13,749   1,159      8.4%  3/24
    California      27,650   2,102      7.6%  3/24
    Washington      33,933   2,221      6.5%  3/23
Indeed, New York State has the highest percentage of positive tests — substantially higher. There must be a factor in play. Could there be a difference in testing (i.e., difference in the test kits? different test protocol?) Did SARS-CoV-2 hit New York State sooner? Is COVID-19 more prevalent due to the population density in the New York City region, as the Governor speculated?
Only a good epidemiological study could really measure the prevalence of SAR-CoV-2 in the community. As to timing, I don’t think we will ever know when SARS-CoV-2 hit our shores. New York City is a major global transportation hub. Even so, Washington and California have strong business and family ties across the Pacific and Pacific rim and have major transportation hubs (Los Angeles, San Francisco, San Diego, Seattle).
If I get a chance today, I’m going to look into our neighbor to the north, Vancouver. Vancouver is also quite connected with Asia and the Pacific rim.
The Washington Department of Health has had difficulties with its COVID-19 database. Although they posted a new number of positive cases, 2,469 as of March 24, the number of negative cases was not updated, showing the same total negative test count as of March 23.
The national picture
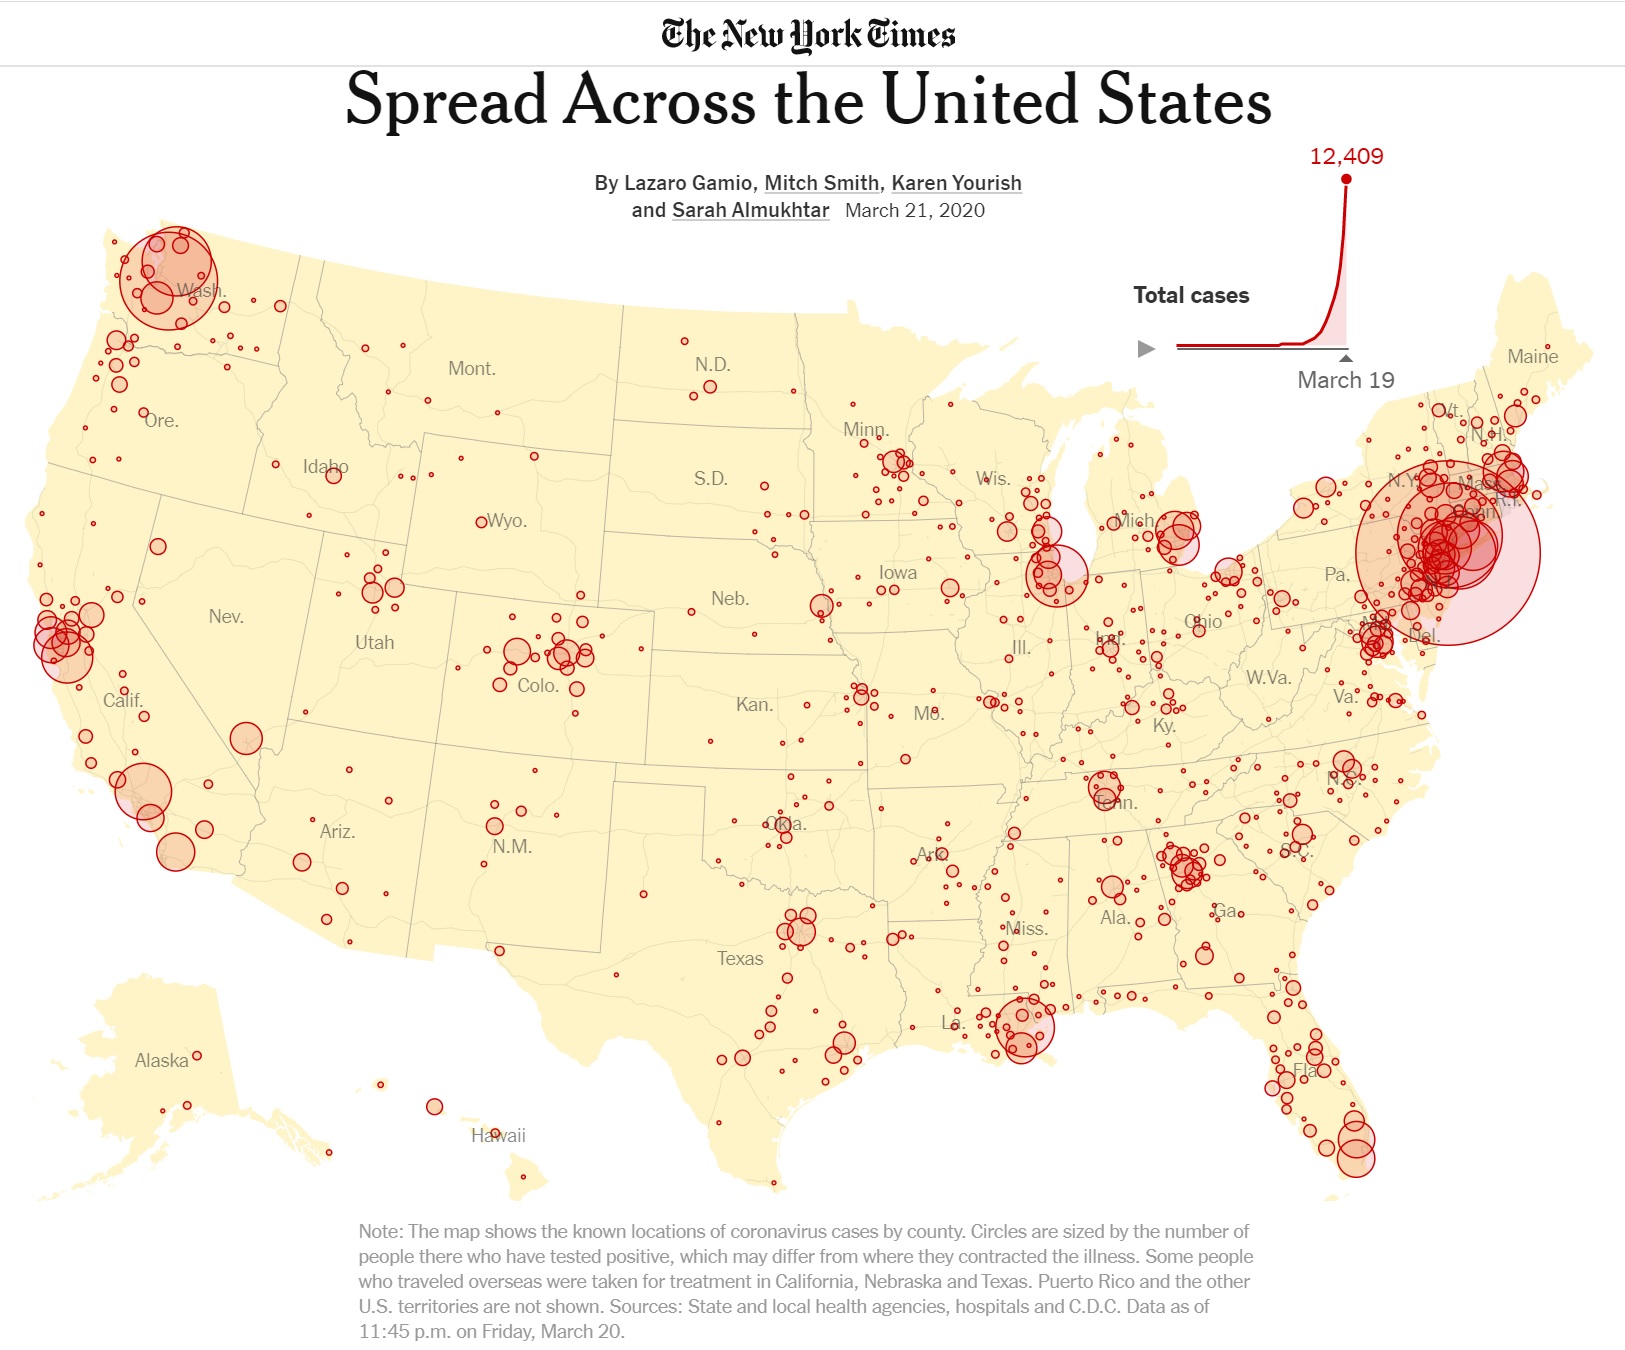
The New York Times has published many informative graphs and simulations during the COVID-19 crisis. The chart below shows the spread of SARS-CoV-2 (the virus) and COVID-19 (the disease caused by SARS-CoV-2) across the United States as of March 19, 2020.
Source: The New York Times
The chart illustrates how population density affects the number of COVID-19 cases. [Click to enlarge.] The biggest circles coincide with the major urban centers in the United States. On the west coast are Seattle-Tacoma-Washington, the San Francisco Bay area, and Los Angeles, for example.
The chart demonstrates why it isn’t appropriate to think numerically about the country as a whole. Sure, Americans want to know how the U.S. is doing overall. However, when it comes to actual COVID-19 containment and mitigation, it’s a local, regional problem. That’s why our county and municipal health departments are so important and local statistics are the most meaningful and practical.
All is not local, however. The urban centers are connected by highways and air routes, giving SARS-CoV-2 passage. As the disease plays out, the coastal urban centers with the greatest population and density will likely succumb first, followed by so-called second tier cities. When the disease subsides in major urban centers, the second tier will maintain active reservoirs of SARS-CoV-2. If major urban centers drop community mitigation (e.g., social distancing) too soon, the active pools in the second tier will cause COVID-19 flare-ups in any major urban center that drops its mitigration too early.
Major urban centers are more tightly connected to global business and commerce than the second tier. SARS-CoV-2 likely arrived much earlier than the second tier and SARS-CoV-2 has probably been circulating in the first tier population for a longer time.
Italy’s land area is 294,140 sq km (square kilometers), roughly the size of Arizona (294,207 sq km). Italy’s population is estimated to be 62,402,659 people (July 2020). California is the most populous state with 39,512,223 residents (July 2019). Overall, Italy has as many people as California and New York State combined in a smaller land mass (Arizona).
Italy’s Lombardy region is, arguably, the Italian region most severely affected by COVID-19. Lombardy is located in northern Italy with the major urban center Milan as its capital.
Lombardy has 10,078,012 people (August 2019). It is the most populated region in Italy. It’s population is roughly the size of Michigan (or North Carolina, or Georgia). Lombardy, by population, would be the tenth largest state in the U.S. Lombardy is 23,844 sq km, roughly the size of West Virginia. Lombardy has a population density of 420 people per sq km.
The city of Milan has 1.369 million people. (The World Fact Book claims 3.140 million people, but it depends on how one draws boundaries.) Milan has a population density of 7,572 people per sq km (2019). That’s roughly the same density as Huntington Park (Los Angeles metro) or Somerville (Boston metro). New York City has a population density of 10,431 people per sq km. [I taught in Somerville; it’s dense.]
Lombardy accounts for 68% of COVID-19 fatalities in Italy. 23% of Italians are 65 or older, making it the second oldest population in the world. (Japan is first.) Age and underlying health conditions are known COVID-19 vulnerabilities. High population density and more elderly people (with existing health issues) are a fatal combination of factors.
Temperature
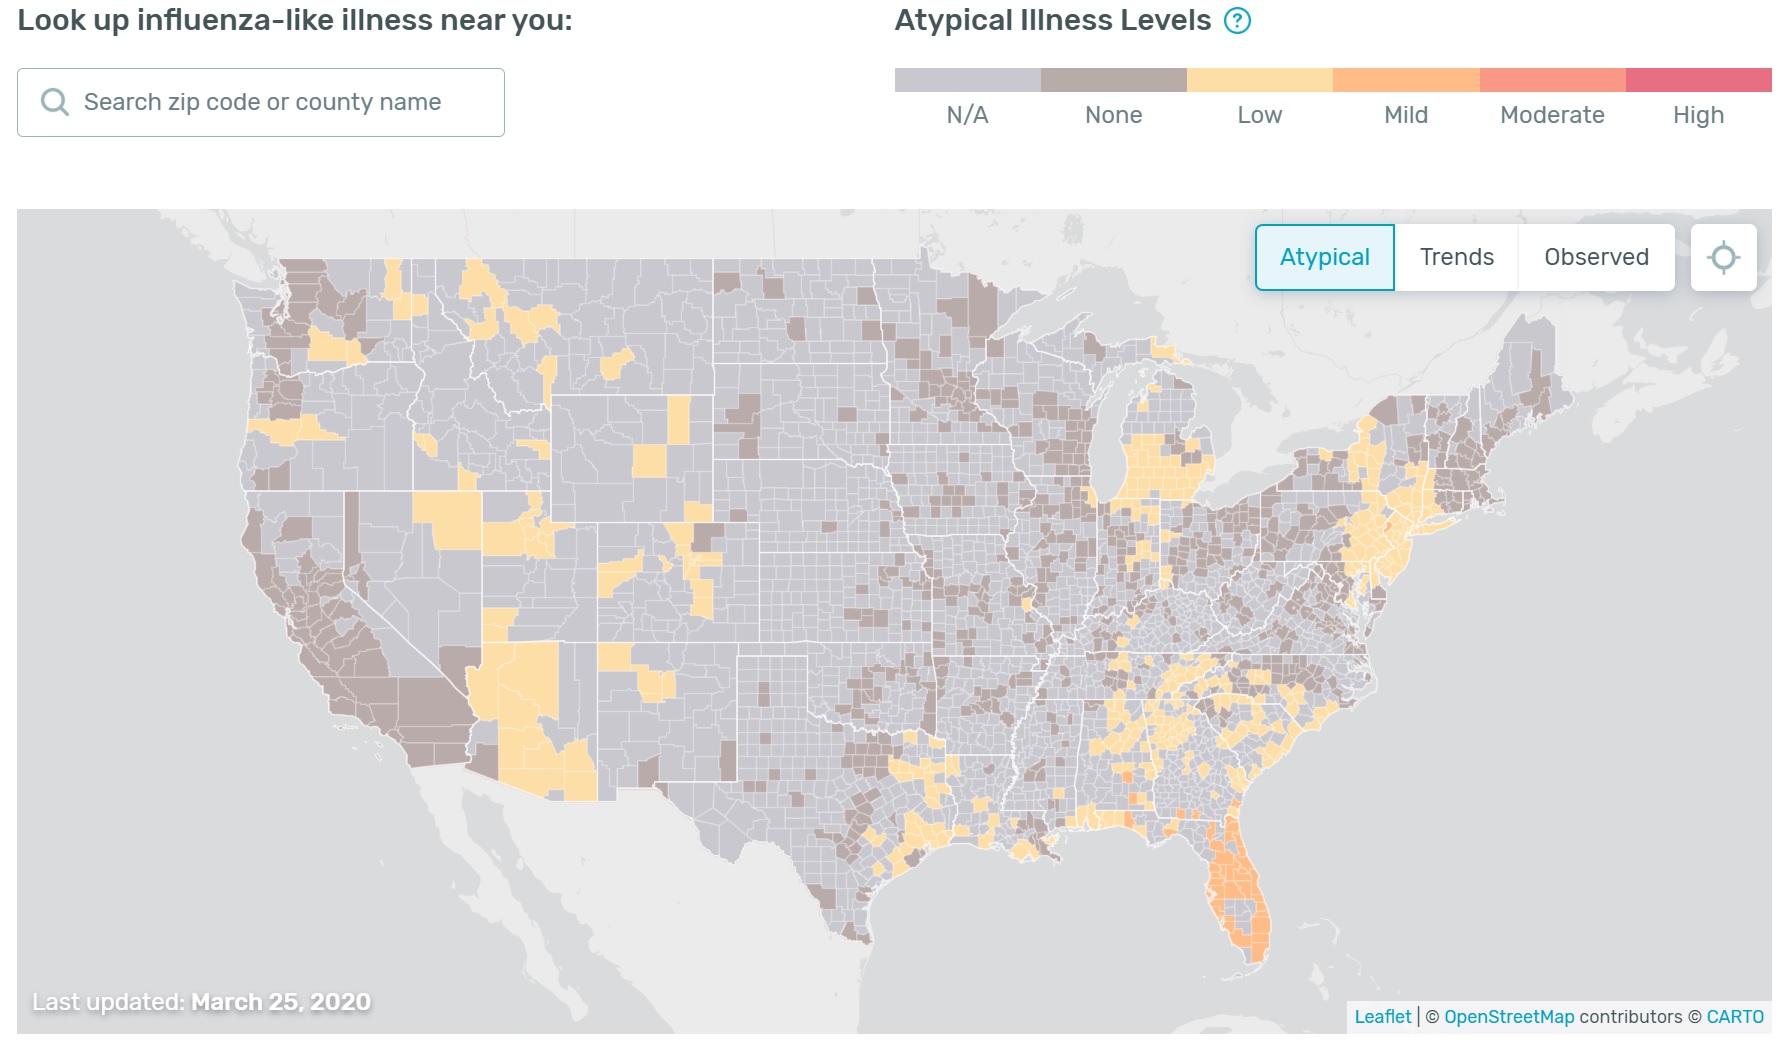
One final observation because it involves maps. The Kinsa US Health Weather Map has received media attention including MSNBC’s The Rachel Maddow Show. (Hi, Rachel.)
The Health Weather Map is a visualization of seasonal illness linked to fever as measured by Kinsa Smart Thermometers. The Kinsa Thermometer connects to your device (and the Kinsa App) via Bluetooth. The Kinsa Thermometer costs about $20-$25 USD retail and requires the Kinsa App for Web communication.
Here is today’s map (March 26). [Click to enlarge.]
Kinsa US Health Weather Map (March 26, 2020)
I look at the Health Weather Map with interest, but take it with a grain of salt. There are two factors to consider.
Although the Kinsa Thermometer is inexpensive, it needs an expensive smart device in order to communicate results via the Web.
It’s not clear how people use the thermometer, i.e., do they take their temperature every day? When they feel sick?
Given the need for a smart device and Internet connection, I’m not sure if Kinsa users represent the population at large. Use of the device may bias results, too. If users take their temperature only when they are sick, then the map will show more high temperatures. Ah, well, I need to dig into their study. [Thank you, Kinsa, for posting your methodology.]
Stay apart, mate, and we’ll both be healthy — P.J. Drongowski
Thank goodness. When I first glanced at the percentage of new positive cases per day (Washington State), I felt optimistic. After reflection, I decided. “Yes, it’s good that the percentage is not increasing rapidly, but even no change is still bad.” Even a constant flow of new patients into the health care system will eventually overwhelm it. A linear curve, as opposed to an exponential curve, merely postpones the day when we exceed capacity.
Someone might say, “Oh, linear isn’t bad.” Yes, it is and here’s why. It’s not like an acute care patient arrives, is given some magic cure and is sent home. Mean duration of hospitalization in Chine was 12.8 days. [Please see “Clinical Characteristics of Coronavirus Disease 2019 in China” in the New England Journal of Medicine.] Even with a so-called linear curve, acute care patients are admitted and stay. Most hospitals are “right sized” during normal times by administrators interested in efficency. So, it doesn’t take long before capacity and staff are exhausted.
China had hospitalization rates ranging from 15% to 20%. In the Chinese epidemic, 41.3% of patients received oxygen therapy and 6.1% received mechanical ventilation.
There is only one advantage to a linear curve vs. exponential — it gives hospitals and other facilities an opportunity to ramp up for the influx of acute care patients. The availability of respirators and ventilators is a critical concern as well as temporary beds and infrastructure for convalescence and recovery.
We need to push the number of new COVID-19 cases downward through social distancing and good hygiene. I’m glad that Governor Inslee has issued a full stay-at-home order. Now, we all need to listen to it and act.
New York City
Governor Cuomo of New York was visibly more alarmed today. I pulled together a quick table of new case and new testing statistics for New York City (NYC).
I’m alarmed, too.
New York City (NYC)
             Cum       New     Cum     New          Percent
Date    Positive  Positive   Tests   Tests  Ratio  Hospital
------  --------  --------  ------  ------  -----  --------
Mar 20      4408      1939   14386    4852  40.0%       18%
Mar 21      6211      1803   19463    5077  35.5%       15%
Mar 22      9045      2832   26389    6927  40.1%       13%
Mar 23     12305      3260   33003    6614  49.3%       13%
Mar 24     14904      2599   38390    5387  48.2%       --
Mar 25     17856      2952   44076    5686  51.9%       12%
Mar 26     21393      3537   51031    6955  50.9%       14%
Mar 27     25398      4005   57954    6923  57.9%       15%
Mar 28     29766      4368   65902    7948  55.0%       --
Mar 29     33768      4002   73104    7202  55.7%       14%
Mar 30     37453      3685      --      --     --       14%

24% of hospitalizations are ICU patients (March 23)
23% of hospitalizations are ICU patients (March 24)
24% of hospitalizations are ICU patients (March 26)
24% of hospitalizations are ICU patients (March 27)
24% of hospitalizations are ICU patients (March 29)
25% of hospitalizations are ICU patients (March 30)
The percentage of new positive cases per day (which takes the ever-varying number of tests into account) for Washington State is around 6.5%. The ratio for New York City is 6 times higher than Washington. (Update: Washington State calls this ratio “Positivity Rate.”)
I fear that NYC is already in the weeds. Folks, NYC is the largest financial center in the United States. So, even if all you care about is money, this is the wrong time to lift restrictions and to restart the American economy. Plain and simple, that’s crazy talk. And, immoral.
Stay distant and stay healthy — P.J. Drongowski
Update quoting CNBC News:
New York and New Jersey are seeing coronavirus attack rates at least five times higher than other parts of the country, a U.S. official in charge of the White House’s pandemic response efforts said Monday.
“The New York metro area of New Jersey, New York City, and parts of Long Island have an attack rate close to one in 1,000,” Dr. Deborah Birx, a physician and the White House coronavirus response coordinator, said at a press briefing Monday evening. The attack rate is the percentage of a population that gets the disease.
She said roughly 28% of the specimens submitted in that region have tested positive for COVID-19, while less than 8% have tested positive for the disease in the rest of the country.
New York is currently the hardest-hit state in the country, ahead of New Jersey, California and Washington state. New York City, alone, accounts for 12,305 of the 20,875 confirmed infections in the state as of Monday morning.